Archive | September 2025

Certain cardiac rhythms can lead to a cardiac arrest or other things & how to prevent it!

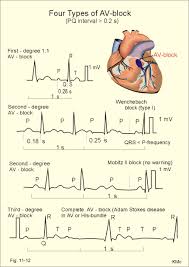
HeartBlocks1

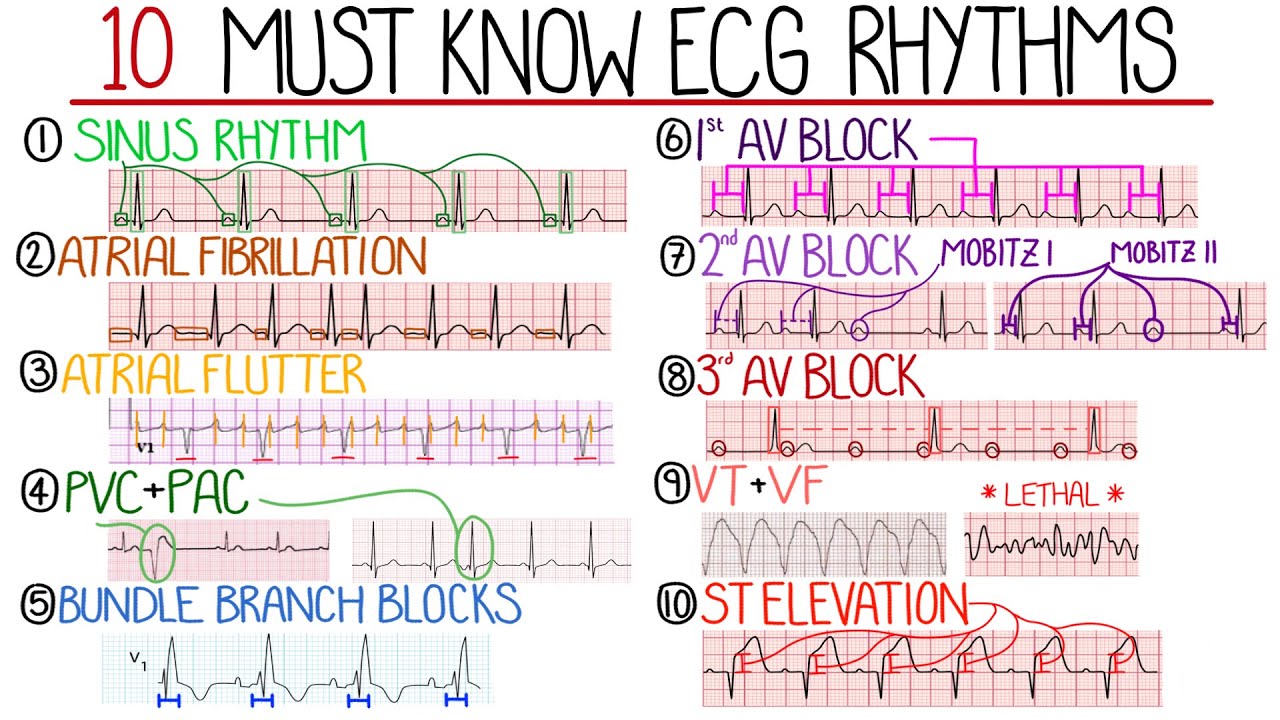
The rhythms above are heart blocks (HB) that occur in the bottom of the upper chambers which can occur in some people. There is 1st degree HB where you can live a completely normal life with but 2nd and 3rd degree HB needs treatment (usually a pacemaker) by cardiologist surgeon.  After treatment with 2nd and 3rd degree HB you can live a completely normal life with follow up with your cardiologist and yearly pacemaker checks.

In this rhythm below the Ventricular Tachycardia is with a point on the top but than flips upside down (commonly called Torsedes Pointes).  This is commonly due to Magnesium Level low and IV Magnesium in the hospital is given 1 to 2 gm.
ventrhy4

This  rhythm above with a pulse=also a rhythm pulsating in different areas of the heart in the ventricles only causing the rhythm not to look identical throughout the tele strip above = Polymorphic V- Tac- meaning the stimulus in the ventricles to make the heart beat is coming from different areas of the ventricles for each beat.  Each jagged tooth is a beat that makes up the whole strip shown above for Ventricular Tachycardia.

Than when the atriums aren’t working as the natural pacemaker that took over for the sinus node but now they don’t work so now the ventricles take over and the rhythms of all ventricle rhythms are with NO p waves since the atriums are not working so no p wave is involved but we have QRS waves but their wide in measurement because the rhythm starts in the ventricles. The rhythms are PVC (Premature Ventricular Contractions), Idioventricular Rhythm, Ventricular tachycardia (Monomorphic and Polymorphic-rhythm getting more irregular. When regular and monomorphic=looking identical with every ventricular beat or contraction as opposed to polymorphic=not looking identical each contraction but each one is a ventricular contraction), Torsades De Pointes Ventricular Tachycardia (the rhythm starts upright but turns upside down but each contraction without a p wave and a wide contraction meaning a ventricular contraction), and Ventricular Fibrillation, to asystole.

Here’s what they look like:

 Accelerated Idioventricular Rhythm

Accelerated idioventricular rhythm occurs when three or more ventricular escape beats appear in a sequence. Heart rate will be 50-100 bpm. The QRS complex will be wide (0.12 sec. or more).

A regular QRS measures less than 0.12 which is with all atriums rhythms.

 Asystole

Asystole is the state of no cardiac electrical activity and no cardiac output. Immediate action is required.

Idioventricular Rhythm

Idioventricular rhythm is a slow rhythm of under 50 bpm. It indicates that then ventricules are producing escape beats.
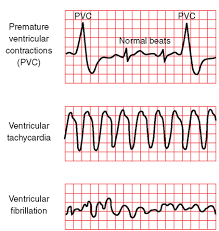
Premature Ventricular Complex-PVC (above 1st strip in #4)

Premature ventricular complexes (PVCs) occur when a ventricular site generates an impulse. This happens before the next regular sinus beat. Look for a wide QRS complex, equal or greater than 0.12 sec. The QRS complex shape can be bizarre. The P wave will be absent.

Premature Ventricular Complex – Bigeminy a QRS after every 2 regular beats

Premature Ventricular Complex – Trigeminy a QRS after every 3 regular beats

Premature Ventricular Complex – Quadrigeminy a QRS after every 4 regular beats

The more PVC’s especially right next to each other can lead to Ventricular Tachycardia to Ventricular Fibrillation if not treated in time.

 Ventricular Fibrillation (in above strip-3rd one)

Ventricular fibrillation originates in the ventricules and it chaotic. No normal EKG waves are present. No heart rate can be observed. Ventricular fibrillation is an emergency condition requiring immediate action.

Ventricular Tachycardia  (in above strip-2nd one)

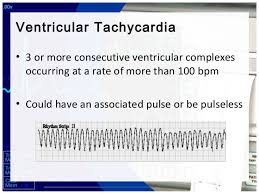
A sequence of three PVCs in a row is ventricular tachycardia. The rate will be 120-200 bpm. Ventricular Tachycardia has two variations, monomorphic and polymorphic. These variations are discussed separately.

Ventricular Tachycardia Monomorphic

Monomorphic ventricular tachycardia occurs when the electrical impulse originates in one of the ventricules. The QRS complex is wide. Rate is above 100 bpm.  Each V tac beat looks identical like in the strip above.

Ventricular Tachycardia Polymorphic

Polymorphic ventricular tachycardia has QRS complexes that very in shape and size. If a polymorphic ventricular tachycardia has a long QT Interval, it could be Torsade de Pointes.  The strip shows the pulses are not identical=polymorphic since the pulse beats are coming from all different areas of the ventricles.

Torsade de Pointes  (the rhythm strip at the top under Heart Blocks)

Torsade de Pointes is a special form of ventricular tachycardia. The QRS complexes vary in shape and amplitude and appear to wind around the baseline.  This is an example or polymorphic ventricular tachycardia.

Ventricular ending line needs to be treated stat to be switched back to atrial rhythm since the heart is missing ½ of the conduction it’s to normally receive from the atriums and if not reversed the heart will go into failure to heart attack or to asystole flat line and go into a cardiac arrest.

With PVCs=Premature Ventricle Contractions asymptomatic we just closely monitor the pt and telemetry the pt is on. Now a pt with PVCs and symtomatic usually meds with 0xygen (sometimes 02 alone resolves it but other times with meds) but if it gets worse into V Tachycardia the treatment is below.

Idioventricular Rhythm (IVR)is usually with a slow brady pulse and needs meds.   Accelerated IVR (AIVR) is usually hemodynamically tolerated and self-limited; thus, it rarely requires treatment.

Occasionally, patients may not tolerate AIVR due to (1) loss of atrial-ventricular synchrony, (2) relative rapid ventricular rate, or (3) ventricular tachycardia or ventricular fibrillation degenerated from AIVR (extremely rare). Under these situations, atropine can be used to increase the underlying sinus rate to inhibit AIVR.

Other treatments for AIVR, which include isoproterenol, verapamil, antiarrhythmic drugs such as lidocaine and amiodarone, and atrial overdriving pacing are only occasionally used today.

Patients with AIVR should be treated mainly for its underlying causes, such as digoxin toxicity, myocardial ischemia, and structure heart diseases. Beta-blockers are often used in patients with myocardial ischemia-reperfusion and cardiomyopathy

With Ventricular rhythms with fast pulse over 100 with symptomatic signs for the patient we may use as simple as valsalva pressure on the neck that medical staff only do but when pt is in asymptomatic (no symptoms) Ventricular Tachycardia (V-Tac) to even medications but when symptomatic if in V-Tac start cardioversion with a pulse if no pulse called pulseless V-Tac we use a defibrillator since there is no pulse there is no QRS to pace with in having the shock hit at the R wave, why? NO PULSE.

Treatment for Torsade de Pointes is Magnesium deficiency and Mag. Supplement given IV 2gms. Usually effective but if necessary the same as above as directed for it with a pulse or the other V Tac. (without a pulse)-See above.

Ventricular Fibrillation is when the ventricles are just quivering and the atriums in any ventricular rhythm doing nothing. The pt needs CPR and ASAP a defibrillator in hopes the shock will knock the rhythm back to a normal sinus or some form of a real rhythm.

Asystole which is a straight line, no pulse and this is CPR with epinephrine or Vasopressin 40 for only the replacement of the 1st or 2nd dose of Epinephrine 1mg. This is given 3-5 minutes (epinephrine). No defibrillation since no pulse. A rhythm may come back and if not the MD will call when CPR stops. Asystole is hard to resolve in most cases highier probability of resolution if in a hospital where close monitoring is done and its detected quicker.

The PURPOSE in treating any rhythm abnormal to the human heart is to reach the goal of a optimal or healthiest rhythm (a normal sinus rhythm , the best rhythm the heart can be in) and if not reaching an atrial rhythm.  We the medical field aim to reach a heart rhythm the patient can live with and hopefully reaching the best NSR-Normal Sinus Rhythm.  Normal sinus rhythm that is a rhythm starting from the upper right chamber extending to the left one and continues down on both sides to the bottom of the ventricles.  This rhythm is giving the most effective oxygen perfusion to the heart to allow it to do its function (pumping good oxygenated blood flow out of the left ventricle at the same time pumping highly carbon dioxide blood from the right side of the heart to the lungs to get more oxygen).   Doing this it allows the human body to get good amounts of oxygen to all our tissues=good overall oxygen perfusion to all tissues.  At the same time what happens is red blood cells from all tissues with mostly used up oxygen from the cell and more carbon dioxide in the cell are also being pumped by the heart to return to the right side  to the lungs to go through this whole process again in getting more oxygen in the RBCs which keeps us alive. A human without oxygen or low oxygen to their tissues or any tissue is going to reach cellular starvation which in turn causes starvation to the tissues (in general) or to a tissue area (Ex. Take the diabetic-regarding the foot to lack of 02 to cyanotic purple tissue to necrotic black tissue=dead to amputated since the tissue is dead.  Remember by gravity the foot is the furthest from the heart).

Cardiac Arrest or Heart Attack are more likely to occur in  a irregular rhythm especially making the heart work to hard being RVR afib in the atriums that can lead easily to ventricular tachycardia to ventricular fibrillation and not treated immediately.

Cardiac Arrest or an abnormal heart rhythm is an electrical problem with the conduction of the heart whereas a Heart Attack can be caused by a blockage of blood.  An example could be the coronary arteries-main arteries of oxygenated blood to the heart that can lead to a bad rhythm due to lack of 0xygen that leads to worse rhythms as the heart gets more stressed out.

For direction many experts like Atlantic Endocrinology states the following:

“You feel fine—no chest pain, no shortness of breath, no obvious red flags. But what if heart disease is developing silently?  It does for many where the cardiac condition was there awhile but no symptoms and the symptoms arise when the condition gets worse for many cardiac Dx’s.  Who wants to go to the doctor when they feel fine but there is always the silent symptoms and not just for cardiac issues but for this topic we will keep to just cardiac issues.

Many people assume a cardiologist is only for the elderly or those with symptoms, yet heart issues often start long before warning signs appear. So, when is the right time to schedule that first cardiac appointment? The answer might be earlier than you think.

Seeing a cardiologist isn’t just for the elderly or those with symptoms—heart disease can develop silently. Men over 40 and women after menopause face increased risk, especially with a family cardiac history of heart disease, high blood pressure, cholesterol, or diabetes. Preventive check-ups before age 60–70 improve outcomes.

Warning signs could definitely be such as chest pain or chest discomfort, shortness of breath or difficulty breathing, continuous headaches, palpitations continuous or intermittent, fatigue, dizziness or swelling or edema, require medical attention. Monitoring blood pressure, cholesterol, and managing lifestyle factors like diet, exercise, and stress are crucial. Those with hereditary or pre-existing heart conditions should see a cardiologist early for specialized care and prevention.”

Now even with rhythms that could lead to a heart attack!   Not that the rhythms were the primary cause of the heart attack but in most cases the rhythm is due to the cardiac condition. 

Now the rhythm can be used in helping the doctor as a preventative measure if found earlier enough to stop the heart attack from occurring! 

Now you know why there are many reasons to see a cardiologist at least yearly from 40 and up in men and post-menopausal in women!  Gave some examples or I would be writing a few novels!

QUOTE FOR TUESDAY:

“As the most commonly performed heart test, an electrocardiogram measures and records the electrical activity of your heart. Also known as an ECG or EKG, this key diagnostic tool provides invaluable and insightful information about the rhythm and function of your heart.

Simply put, an EKG is a “heart tracing” that offers a reliable (if not preliminary) snapshot of your cardiovascular health.

An EKG is a painless and noninvasive test that measures your heart’s electrical efficiency as it beats. As one of the fastest informational or diagnostic heart tests available, EKG testing can usually be completed in just five minutes.

To conduct an EKG test, a patient attaches up to 12 small, flat, sticky patches called electrodes at various points on your chest, arms, and legs. The electrodes are connected to a monitor that registers your heart’s electrical activity over the course of the exam.

During standard EKG testing, you lie still on a table as the electrodes detect and transmit the electrical activity of your heart to the monitor. EKG testing may also be used to measure and record your heart’s electrical efficiency under stress and through recovery.

The electrical activity of your heart doesn’t just drive your heartbeat, it also sets the rhythm and rate of that beat. A healthy heart usually has a regular beat that’s powered by steady electrical patterns, while a diseased or dysfunctional heart is more likely to have an irregular beat that’s controlled by fast, slow, or erratic electrical patterns.

Every single heartbeat is driven by an electrical impulse, or wave, that causes your heart to contract; each vital contraction keeps blood flowing seamlessly through your body.

An EKG monitors the strength, timing, and efficiency of this wave as it travels through the upper chambers of your heart to the lower chambers. It also monitors the electrical recovery between waves, or your heart’s momentary return to a resting state between each beat.”

ECCA Cardiologists (What an EKG Test Can Tell Your Doctor About Your Heart)

What cardiac rhythms tells your doctor about your heart!

Heart Beat symbol design element

Why cardiac monitoring can be vital important in quickly telling the doctors and nurses very important messages in what is going on with the patient’s heart and overall condition problem (Example A Myocardial Infarction or even to Cardiac Arrest).

Cardiac monitoring is a great way for doctors to understand a patients’ overall heart health, and can provide enough information to quickly and accurately helping the doctor or nurse as a diagnostic tool based on several details within a heart rhythm. While each arrhythmia monitoring device is a little different, these details are essential in diagnosing any underlying and potentially life-threatening events.

Your heart can have the best rhythm it can be in called Normal Sinus Rhythm which is a rhythm that is produced by the sinus node (SA node) that is the human pacemaker of the heart in out right upper atrium.  It starts a impulse (think of it as a message) that starts from the SA node and goes down the right atrium across to the left atrium (the upper chambers of the heart) with contiuing to send both impulses down to the bottom chambers of the heart which we call Ventricles creating the sound we all know the heart make called “lub dub”. This sound is creating when our heart valves open and close between the heart to allow complete fill up and release for the cardiac filling of our blood from top chambers to bottom and out of the heart to our circulation to send oxygenation out to all our tissues from feet to brain and back to lungs where our red blood cells carry the oxygen to tissues but take carbon dioxide back to the lungs for an exchange of new oxygen we breath in to exchange the carbon dioxide for new oxygen in the red blood cells and is send to the heart sent out back to our circulation to keep our body tissues oxygenated.  Without oxygenation that would be red blood cell starvation resulting into death for the human body.

There are times the SA node does not work for some reasons which causes the heart to start sending impulses from areas lower than where the SA node sits in the heart, in the upper right area of the heart.  Now some rhythms under the SA node can live a normal life with being checked up by a Cardiologist preferably or a Primary Care Doctor but know the Cardiologist will probably pick up before any other MD, if numerous years of experience.

Here is the basics to know about telemetry monitoring and your heart rate (also known as pulse):

1. Arrhythmias: Ambulatory heart monitors can be assigned for short-term use (24 to 72 hours) or for long-term use (up to 30 days or more) depending on what your doctor needs to know. Many cardiac monitoring devices record the ups and downs of your heartbeat to determine the presence of any irregularities in your rhythm that could be associated with an arrhythmia that’s new but possibly easily treatable or even curable to dangerous possibly or any underlying conditions.  There’s a device that we call holter monitor.  This device is what you wear for days and bring back to your doctor with leaving on 24hrs or  couple of days till you take off when the MD tells you too.  Than there is continuous telemetry monitoring in the hospital that records on the unit computer the patient usually is on.  This the MD reviews when you come back to his office with the holter monitor or the MD reviews daily or more when in the hospital.  This helps direct the MD in your care since it is a diagnostic tool for him or her.

2. Heart Rate: Your heart rate is the number of times your heart beats per unit of time, and can vary depending on your activities, sleep, and even what you eat. If it gets too low or too high when performing a specific activity, it’s essential that your doctor knows about it. A normal resting heart rate for adults ranges from 60 to 99 beats a minute.  The lower the better but usually not more than 50 if you have been in the heart rate or pulse of 50’s all your life due to being an athelete (some even in there 40’s) but if you have symptoms like dizzy, weakness, change in mental status, chest pain/discomfort, to indigestion that just won’t go away SEE THE MD; especially if the HR or pulse rate is new in a low rate that you are in.

3. P-wave analysis: On the telemetry monitor what MD’s, nurses and even technicians see are rhythm waves that is represented by names for each aspect of the wave we study.  The first wave if in normal sinus rhythm or some type of sinus rhythm we see what we call a p-wave represents the spread of electrical activity over the atrium, and normally lasts less than 0.11 seconds that derived from the SA node.  This is how sinus rhythms got their names.  An abnormally long p-wave occurs when it takes extra time for the electrical wave to reach the entire atrium.  This is the area right before that bigger wave we call QRS wave.   The prolongation for the PR interval signifies usually some type of AV block.  This occurs down at the valves between the upper chambers (atriums) and lower chambers (ventricles).  Ventricle rhythms means their is no impulse going through the atrium or we would see a atrium rhythm so now the ventricles take over to make a rhythm showing Ventricular Rhythms.  These are dangerous rhythms.

4. Morphology: This refers to the form of cardiac rhythms and how they differ depending on underlying conditions. The morphology of a heart rhythm can be observed as a series of deflections away from the baseline of an ECG, and can vary if you have any type of condition that could affect your heart  (Let’s say heart failure to even drugs like Cocaine which is famous for speeding the heart up commonly know for putting patients in atrial RVR; meaning atrial fibrillation but at a high heart rate in the atriums putting your pulse at a HR of 150 to 250 and can lead to a heart attack.

Cardiac and arrhythmia monitoring solutions means that you can start treatment much sooner. Your heart monitor provides your physician with data necessary for diagnoses for a wide range of populations including geriatric, diabetic and pediatric patients, all age groups.

QUOTE FOR THE WEEKEND:

“Other than skin cancer, prostate cancer is the most common cancer in men in the United States.

Prostate cancer can be a serious disease, but most men diagnosed with prostate cancer do not die from it. In fact, more than 3.5 million men in the United States who have been diagnosed with prostate cancer at some point are still alive today.

The prostate cancer death rate declined by about half from 1993 to 2022, most likely due to earlier detection and advances in treatment. In recent years, the decline in the death rate has slowed, likely reflecting the rise in cancers being found at an advanced stage.”

American Cancer Society (Key Statistics for Prostate Cancer | Prostate Cancer Facts | American Cancer Society)

QUOTE FOR FRIDAY:

“The American Cancer Society’s estimates for prostate cancer in the United States for 2025 are:

  • About 313,780 new cases of prostate cancer
  • About 35,770 deaths from prostate cancer

The number of prostate cancers diagnosed each year declined sharply from 2007 to 2014, coinciding with fewer men being screened because of changes in screening recommendations. Since 2014, however, the incidence rate has increased by 3% per year.

Prostate cancer remains the second-leading cause of cancer death in American men, behind only lung cancer. About 1 in 44 men will die of prostate cancer. 

About 1 in 8 men will be diagnosed with prostate cancer during their lifetime. But each man’s risk of prostate cancer can vary, based on his age, race/ethnicity, and other factors.

Prostate cancer can be a serious disease, but most men diagnosed with prostate cancer do not die from it. In fact, more than 3.5 million men in the United States who have been diagnosed with prostate cancer at some point are still alive today.

The prostate cancer death rate declined by about half from 1993 to 2022, most likely due to earlier detection and advances in treatment. In recent years, the decline in the death rate has slowed, likely reflecting the rise in cancers being found at an advanced stage.”

American Cancer Society (Key Statistics for Prostate Cancer | Prostate Cancer Facts | American Cancer Society)


QUOTE FOR THURSDAY:

“In an extensive review, the team found that the early life “exposome,” which encompasses an individual’s diet, lifestyle, weight, environmental exposures, and microbiome, has changed substantially in the last several decades. They hypothesize that factors like the Western diet and lifestyle may be contributing to the rise in early onset cancer. The team acknowledged that this increased incidence of certain cancer types is, in part, due to early detection through cancer screening programs. They couldn’t precisely measure what proportion of this growing prevalence could solely be attributed to screening and early detection. However, they noted that increased incidence of many of the 14 cancer types is unlikely due to enhanced screening alone.

Possible risk factors for early onset cancer included alcohol consumption, sleep deprivation, smoking, obesity, and eating highly processed foods. Surprisingly, researchers found that while adult sleep duration hasn’t drastically changed over the several decades, children are getting far less sleep today than they were decades ago. Risk factors such as highly processed foods, sugary beverages, obesity, Type 2 diabetes, sedentary lifestyle, and alcohol consumption have all significantly increased since the 1950s.

“Among the 14 cancer types on the rise that we studied, eight were related to the digestive system. The food we eat feeds the microorganisms in our gut,” said Ugai. “Diet directly affects microbiome composition and eventually these changes can influence disease risk and outcomes.”

“https://news.harvard.edu/gazette/story/2022/09/researchers-report-dramatic-rise-in-early-onset-cancers/

QUOTE FOR WEDNESDAY:

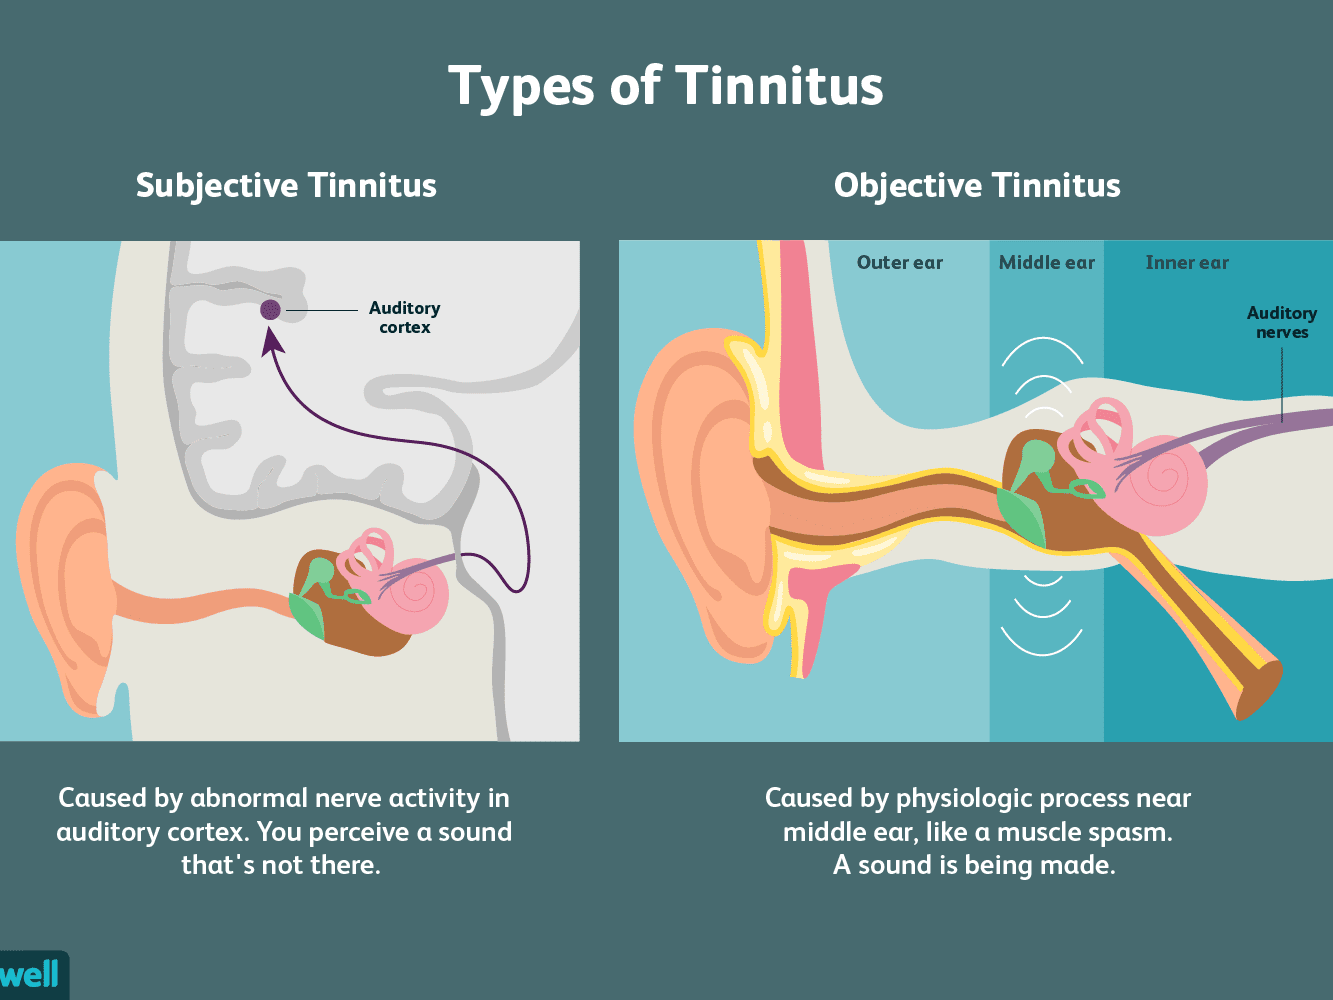
“Increasingly, Harvard Medical School scientists are finding evidence that some people have “hidden” hearing loss: damage to the auditory nerve — which carries sound signals from the ear to the brain — that isn’t picked up by conventional tests.

For people with measurable hearing loss, getting hearing aids sometimes reduces the perception of tinnitus. But hearing aids aren’t recommended for people with normal hearing test results — even if your doctor suspects hidden hearing loss — since we don’t have tests outside of research labs to measure it.

Still, the new evidence linking hidden hearing loss and tinnitus offers hope for people with tinnitus. “When you have hidden hearing loss, only a portion of the auditory nerve has degenerated. Another portion remains alive for years or decades. And a number of experiments by others have found that it’s possible to regenerate nerve fibers in animal models,” Maison says. “If we can one day regenerate those fibers in humans, perhaps it might bring back missing information to the brain, reducing its hyperactivity and the perception of tinnitus.”

Until that day comes — and it’s unclear when or if it will — we have only limited ways to cope with the problem.”

Harvard Health Publishing / Harvard Medical School

Hearing Loss=Tinnitus, learn how health impacts the diagnosis and some facts about hearing loss!

Men are more likely to experience hearing loss than women.

Of adults ages 65 and older in the United States, 12.3 percent of men and nearly 14 percent of women are affected by tinnitus. Tinnitus is identified more frequently in white individuals and the prevalence of tinnitus in almost twice as frequent in the South as in the Northeast.

Approximately 17 percent (36 million) of American adults report some degree of hearing loss.

There is a strong relationship between age and reported hearing loss: 18 percent of American adults 45-64 years old, 30 percent of adults 65-74 years old, and 47 percent of adults 75 years old or older have a hearing loss.

About 2 to 3 out of every 1,000 children in the United States are born deaf or hard-of-hearing. Nine out of every 10 children who are born deaf are born to parents who can hear.

The NIDCD estimates that approximately 15 percent (26 million) of Americans between the ages of 20 and 69 have high frequency hearing loss due to exposure to loud sounds or noise at work or in leisure activities.

Only 1 out of 5 people who could benefit from a hearing aid actually wears one.

Three out of 4 children experience ear infection (otitis media) by the time they are 3 years old.

Roughly 25 million Americans have experienced tinnitus.

Approximately 188,000 people worldwide have received cochlear implants. In the United States, roughly 41,500 adults and 25,500 children have received them.

Approximately 4,000 new cases of sudden deafness occur each year in the United States. Hearing loss affects only 1 ear in 9 out of 10 people who experience sudden deafness. Only 10 to 15 percent of patients with sudden deafness know what caused their loss.

Approximately 615,000 individuals have been diagnosed with Ménière’s disease in the United States. Another 45,500 are newly diagnosed each year.

Approximately 3 to 6 percent of all deaf children and perhaps another 3 to 6 percent of hard-of-hearing children have Usher syndrome. In developed countries such as the United States, about 4 babies in every 100,000 births have Usher syndrome.

One out of every 100,000 individuals per year develops an acoustic neurinoma (vestibular schwannoma).

High levels of cotinine, the chemical that indicates exposure to tobacco smoke and second-hand smoke has been directly linked to higher risks of some types of hearing loss. **

More than 500 million people around the world are experiencing some form of hearing loss right now. Are you one of them?

Share :

If you have hearing loss, you are not alone. About one in six people experience some degree of hearing impairment over the course of their lives.

The effects may not be obvious…

Hearing loss affects people in different ways. Left undiagnosed or untreated, it can damage communications and erode relationships. Over time, hearing loss may degenerate from a strictly physical condition to a psychological one, which is just one of the reasons it is so important to seek a solution promptly. For most people with hearing loss, there is help. Properly fitted hearing aids improve communication for at least 90 percent of people with hearing loss.[1]

The cause of hearing loss may not be clear…

Hearing loss is not just the result of attending loud concerts or a factor of the aging process. Illness and infections can also play a part in damaging your hearing. A University of Wisconsin Medical School 2001 study[2] revealed that hearing loss occurred in nearly 80% of those who may have suffered from a heart attack. They further determined that individuals who exercised at least once a week experienced a 32 percent reduction in the risk of suffering from hearing loss compared to those who did not work out.

Other health issues associated with either temporary or permanent hearing loss include the following:

Sluggish or poor blood flow to the ear

High blood pressure

Sickle Cell Disease

Diabetes

Screenings for diabetes and other conditions typically do not include hearing tests. If you have one of these conditions, it’s probably a good idea to ask for a referral to a hearing care professional who can conduct a hearing screening to see if you are suffering from any kind of hearing loss.

Many other factors can lead to hearing loss, including your family history, repeated exposure to loud noises, injuries, and smoking.

Men are more likely to experience hearing loss than women.

Of adults ages 65 and older in the United States, 12.3 percent of men and nearly 14 percent of women are affected by tinnitus. Tinnitus is identified more frequently in white individuals and the prevalence of tinnitus is almost twice as frequent in the South as in the Northeast.

Approximately 17 percent (36 million) of American adults report some degree of hearing loss.

There is a strong relationship between age and reported hearing loss: 18 percent of American adults 45-64 years old, 30 percent of adults 65-74 years old, and 47 percent of adults 75 years old or older have a hearing loss.

About 2 to 3 out of every 1,000 children in the United States are born deaf or hard-of-hearing. Nine out of every 10 children who are born deaf are born to parents who can hear.

The NIDCD estimates that approximately 15 percent (26 million) of Americans between the ages of 20 and 69 have high frequency hearing loss due to exposure to loud sounds or noise at work or in leisure activities.

Only 1 out of 5 people who could benefit from a hearing aid actually wears one.

Three out of 4 children experience ear infection (otitis media) by the time they are 3 years old.

Roughly 25 million Americans have experienced tinnitus.

Approximately 188,000 people worldwide have received cochlear implants. In the United States, roughly 41,500 adults and 25,500 children have received them.

Approximately 4,000 new cases of sudden deafness occur each year in the United States. Hearing loss affects only 1 ear in 9 out of 10 people who experience sudden deafness. Only 10 to 15 percent of patients with sudden deafness know what caused their loss.

Approximately 615,000 individuals have been diagnosed with Ménière’s disease in the United States. Another 45,500 are newly diagnosed each year.

Approximately 3 to 6 percent of all deaf children and perhaps another 3 to 6 percent of hard-of-hearing children have Usher syndrome. In developed countries such as the United States, about 4 babies in every 100,000 births have Usher syndrome.

One out of every 100,000 individuals per year develops an acoustic neurinoma (vestibular schwannoma).

High levels of cotinine, the chemical that indicates exposure to tobacco smoke and second-hand smoke has been directly linked to higher risks of some types of hearing loss. **

More than 500 million people around the world are experiencing some form of hearing loss right now. Are you one of them?

References:

1-World Health Organization. http://www.who.int/mediacentre/factsheets/fs300/en/

2-Torre P 3rd, Cruickshanks KJ, Klein BE, Klein R, Nondahl DM. (2005). The association between cardiovascular disease and cochlear function in older adults. http://jslhr.asha.org/cgi/content/abstract/48/2/473

3-National Institute on Deafness and Other Communication Disorders (NIDCD).


QUOTE FOR TUESDAY:

“Viral hemorrhagic (hem-uh-RAJ-ik) fevers are infectious diseases that can be life-threatening. They can damage the walls of tiny blood vessels, making them leak. And they can keep the blood from clotting.

Some viral hemorrhagic fevers include:

  • Crimean-Congo.
  • Dengue.
  • Ebola.
  • Hantavirus.
  • Lassa.
  • Marburg.
  • Yellow fever.

These diseases most often happen in tropical areas, such as Central Africa. In the United States, most people who get them have traveled to one of those areas.”

MAYO  CLINIC (Viral hemorrhagic fevers – Symptoms and causes – Mayo Clinic)

What is Hemorrhagic Fever”, also called VHF meaning Viral Hemorrhagic!


Viral hemorrhagic fevers (VHFs) are a group of illnesses caused by four families of viruses. These include the Ebola and Marburg, Lassa fever, and yellow fever viruses. VHFs have common features: they affect many organs, they damage the blood vessels, and they affect the body’s ability to regulate itself. Some VHFs cause mild disease, but some, like Ebola or Marburg, cause severe disease and death.

VHFs are found around the world. Specific diseases are usually limited to areas where the animals that carry them live. For example, Lassa fever is limited to rural areas of West Africa where rats and mice carry the virus.

The risk for travelers is low, but you should avoid visiting areas where there are disease outbreaks. Because there are no effective treatments for some of these viral infections, there is concern about their use in bioterrorism.

These diseases most commonly occur in tropical areas. In the United States, people who get them usually have recently traveled to one of those areas.

There’s no cure for viral hemorrhagic fevers. There are vaccines for only a few types. Until additional vaccines are developed, the best approach is prevention.

Symptoms

Signs and symptoms of viral hemorrhagic fevers vary by disease. In general, early signs and symptoms can include:

  • Fever
  • Fatigue, weakness or general feeling of being unwell
  • Dizziness
  • Muscle, bone or joint aches
  • Nausea and vomiting
  • Diarrhea

Symptoms that can become life-threatening

More-severe symptoms include:

  • Bleeding under the skin, in internal organs, or from the mouth, eyes or ears
  • Nervous system malfunctions
  • Coma
  • Delirium
  • Kidney failure
  • Respiratory failure
  • Liver failure

Causes

Viral hemorrhagic fevers are spread by contact with infected animals or insects. The viruses that cause viral hemorrhagic fevers live in a variety of animal and insect hosts. Most commonly the hosts include mosquitoes, ticks, rodents or bats.

Some viral hemorrhagic fevers can also be spread from person to person.

Stayed tune tomorrow learning more in Part II on Hemorrhagic Fever!