
Archive | February 2025

QUOTE FOR FRIDAY:

“Coronary artery disease (CAD)

  • Coronary heart disease is the most common type of heart disease. It killed 371,506 people in 2022.1
  • About 1 in 20 adults age 20 and older have CAD (about 5%).3
  • In 2022, about 1 out of every 5 deaths from cardiovascular diseases (CVDs) was among adults younger than 65 years old.1

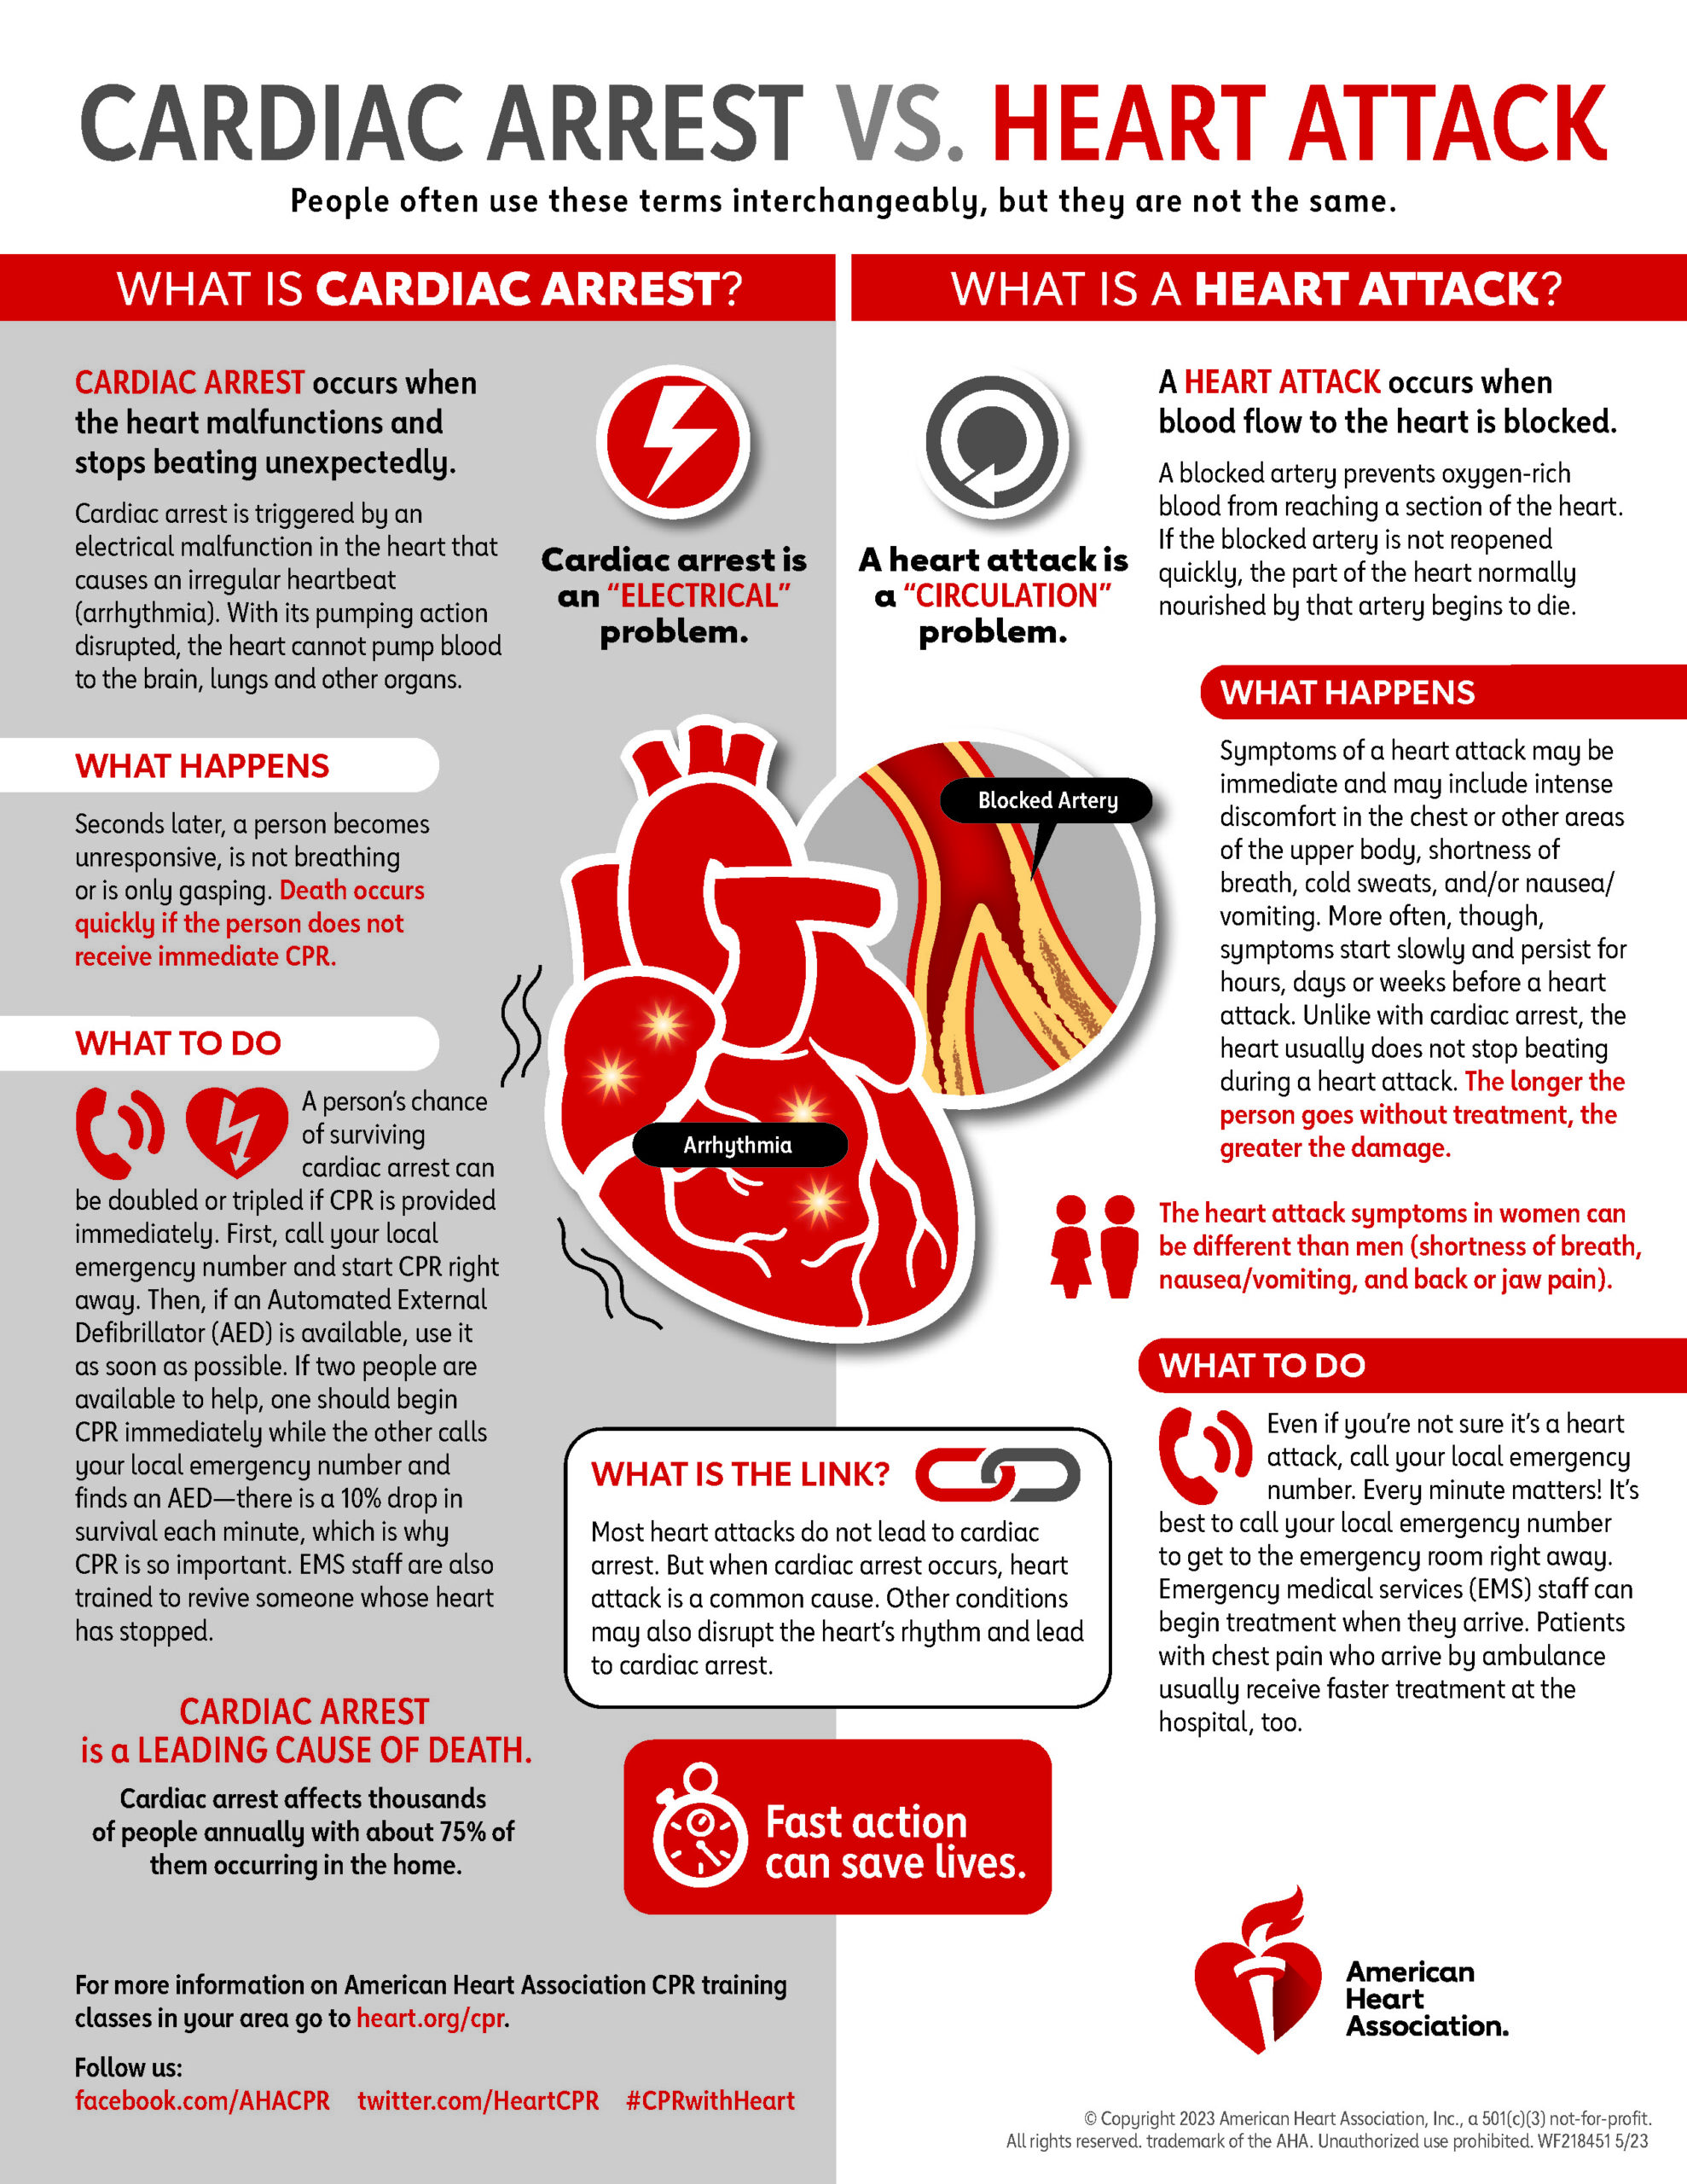
Heart attack

  • In the United States, someone has a heart attack every 40 seconds.3
  • Every year, about 805,000 people in the United States have a heart attack.3 Of these, 605,000 are a first heart attack, and 200,000 happen to be people who have already had a heart attack.3
  • About 1 in 5 heart attacks are silent—the damage is done, but the person is not aware of it.”

Centers for Disease Prevention – CDC (Heart Disease Facts | Heart Disease | CDC)

QUOTE FOR THURSDAY:

“Knowledge is power. If you understand the risks for heart attack, you can take steps to improve your health.

Risk factors are traits and lifestyle habits that can increase your chance of having a heart attack. So, it’s important to know them. You can change some risk factors, some you can’t.

It’s important to know your risk factors for a heart attack.

  • You can control some risk factors, such as tobacco use, physical activity, blood pressure, blood cholesterol and blood glucose.
  • Work with your health care team to manage your risk of heart disease.”

American Heart Association (Understand Your Risks to Prevent a Heart Attack | American Heart Association)

What are the risk factors for myocardial infarction/heart attack?


Continuation of February being the month of the heart I decided to cover the risks of a myocardial infarction (heart attack).

People who are at risk for the development of coronary artery disease and myocardial infarction include those who fall into any of the categories listed below:

-People with a history of heart disease.

-Males.

-Smokers.

-People with high cholesterol.

-People with high blood pressure.

-Obese people.

-People with diabetes.

-People who suffer stress.

-People who live a sedentary life style.

-Heredity is a powerful factor that contributes to early heart disease. Being male is a risk factor, but the incidence of heart disease in women increases dramatically after menopause.

-The risk factors to concentrate upon are those that can be modified. These include cigarette smoking, high blood pressure, cholesterol, obesity, sedentary life style and stress. Cigarette smoking causes many deaths from myocardial infarction and other heart diseases. Smoking contributes to almost half of the heart attacks of women under age 55.

-Stopping smoking can greatly reduce your chances of having a heart attack. Controlling blood pressure can reduce your risk of heart attack. Lowering cholesterol to safe levels through diet and medications can reduce your risk and may even lead to some regression of the plaques already present. Lean body weight and a regular exercise program are helpful.

-If you are diabetic, precise control of your diabetes will help reduce your risk of blood vessel damage due to diabetes. Stress is a risk factor that is common, difficult to quantify and difficult to control effectively over time. Methods of stress reduction include meditation, regular exercise, time management, and a supportive environment.

How is a heart attack diagnosed?

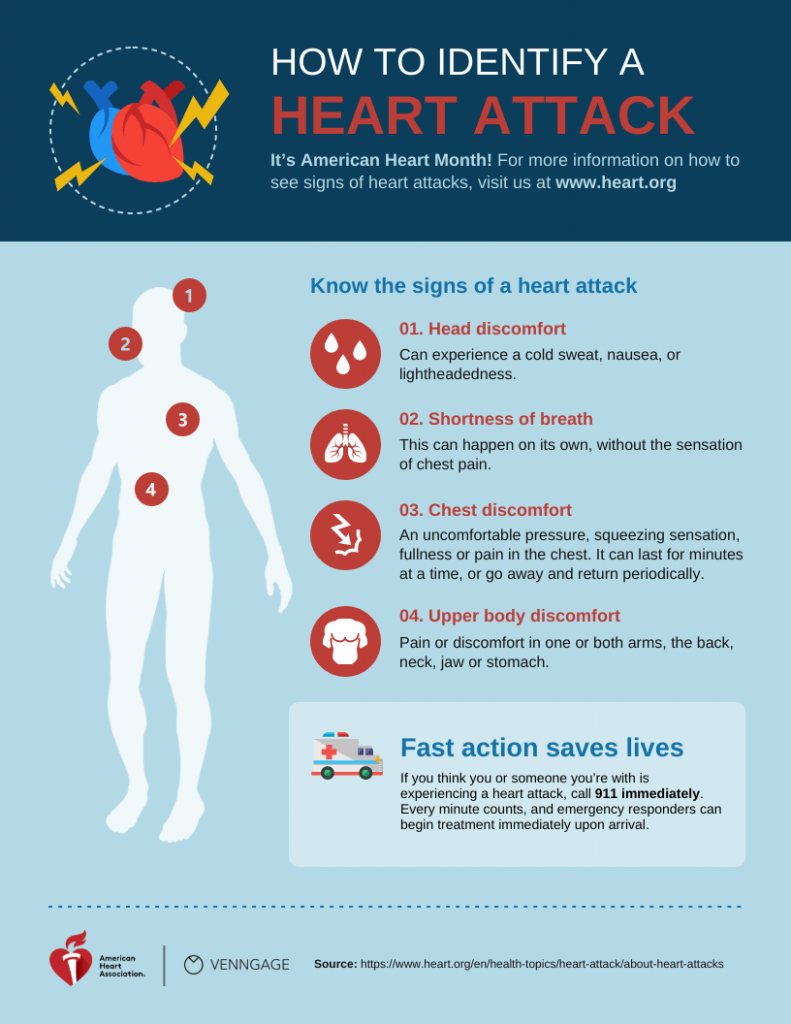
Chest pain is the most common symptom of a heart attack. The chest pain is usually a burning or pressure sensation beneath the mid or upper breast bone. The pain may radiate into the upper mid back, neck, jaw or arms. The pain may be severe but often is only moderate in severity.

There may be associated shortness of breath or sweating. If patients have had angina previously, the heart attack pain will feel the same as their usual angina only stronger and more prolonged. If you have a pain like this that lasts longer than 15 minutes, it is best to be evaluated immediately.

Calling your medic unit is the fastest and safest way to ask for help. If you have symptoms like this that wax and wane, this is often a warning sign that a heart attack is about to occur and prompt medical attention is needed.

Once you are in an emergency room or a doctor’s office an electrocardiogram (ECG or EKG) will be obtained. This is often helpful in diagnosing a heart attack. Sometimes, however, the test is normal even when the heart injury is present but usually a great diagnostic tool.

When heart cells die, certain enzymes present in heart cells are released into the bloodstream that serve as a marker of heart injury (troponin I and CPK or CK-MB). These enzymes can be measured by blood tests. The amount of enzyme released into the blood stream also helps assess how much heart damage has occurred.

TREATMENT:

The best way to limit the size of a heart attack is to restore the flow of blood to the heat muscle as fast as possible. There are two basic methods to do this.

Because most heart attacks are caused by clots forming within the coronary artery, dissolving the clot quickly will restore blood flow. Drugs called thrombolytics are quite effective.

The sooner these drugs are given, the quicker the blood flow will be restored. An alternative method involves the use of balloon angioplasty.

This involves taking the heart attack victim promptly to the cardiac cath lab in the hospital.

An angiogram is performed to show the blocked blood vessel leading to the heart attack. Then a balloon catheter is placed across the blockage and flow is restored.

Sometimes a stent (a device that assists in holding the blood vessel open) is placed to create a large channel.

Smaller heart attacks, often those not producing significant abnormalities on the ECG are often treated with bedrest and blood thinners such as heparin as well as drugs to reduce the work the heart does.

These heart attacks are called non-transmural myocardial infarctions. Before discharge, x-ray studies of the heart arteries are often carried out to see if angioplasty or surgery will be necessary.

Following thrombolytic (clot reducing) therapy, angiogram are often performed to outline the coronary anatomy to help determine if additional therapy such as angioplasty or bypass surgery is indicated. This may be done during the initial hospitalization or later as an outpatient procedure based on the severity of results in the diagnostic tooling the MD orders (tests).


QUOTE FOR WEDNESDAY:

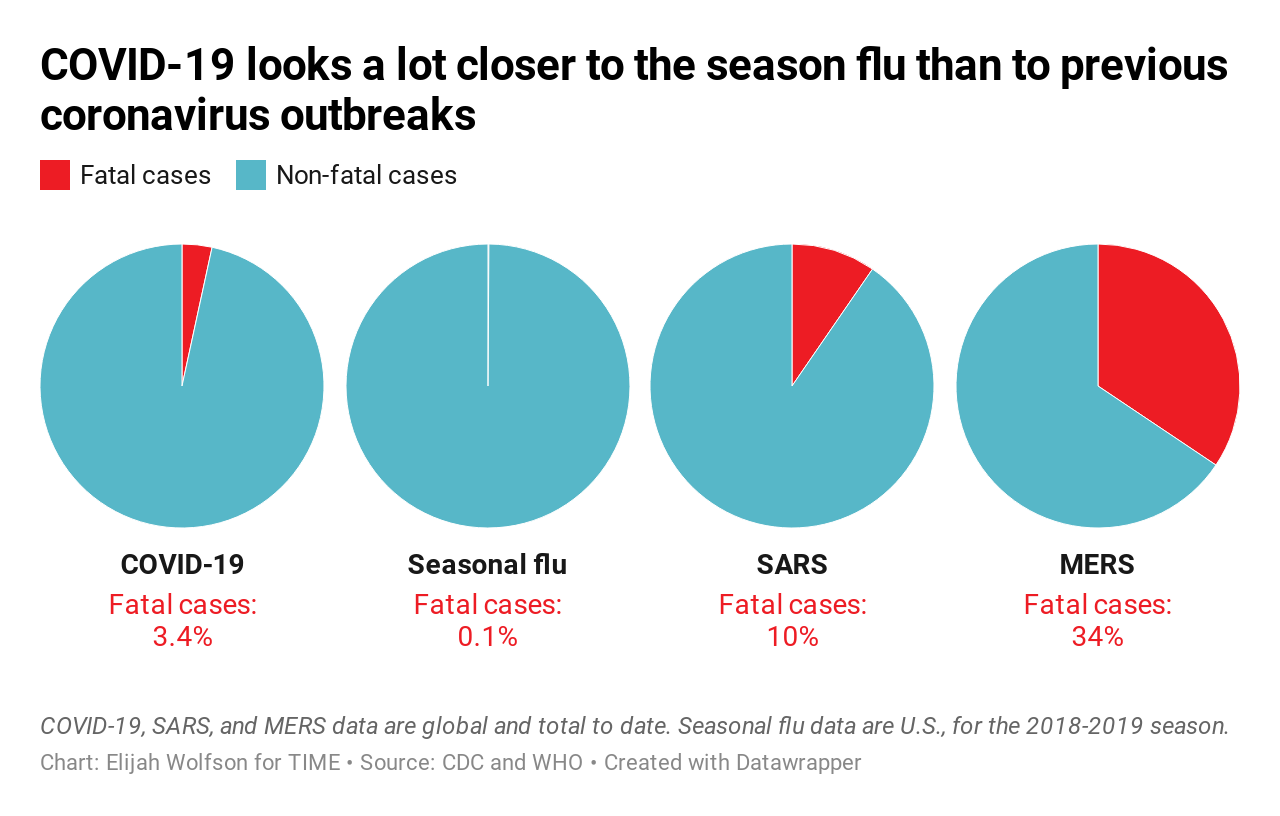
“SARS (severe acute respiratory syndrome, SARS-CoV-1) was a respiratory illness that spread in many countries around the world in 2002 and 2003. For many people, SARS caused flu-like symptoms (like fever and headache), but it progressed to severe illness in about 10% to 20% of people during the outbreak.

More than 8,000 people in 29 countries had SARS during the 2002-2003 outbreak. There was a small outbreak related to occupational exposure in 2004. Preventive measures stopped its spread, and only nine people were infected. There haven’t been any reported cases since then.

A virus called SARS-associated coronavirus (SARS-CoV-1) causes SARS.”

Cleveland Clinic (Severe Acute Respiratory Syndrome (SARS): Cause & Treatment)

What is SARS that first occurred February 2003 in China?

  4 days ago

World Health Organization on this disease SARS coronavirus:

Severe acute respiratory syndrome (SARS) is a viral respiratory disease caused by a SARS-associated coronavirus. It was first identified at the end of February 2003 during an outbreak that emerged in China and spread to 4 other countries.

The virus identified in 2003. SARS-CoV is thought to be an animal virus from an as-yet-uncertain animal reservoir, perhaps bats, that spread to other animals (civet cats) and first infected humans in the Guangdong province of southern China in 2002.

Transmission

An epidemic of SARS affected 26 countries and resulted in more than 8000 cases in 2003. Since then, a small number of cases have occurred as a result of laboratory accidents or, possibly, through animal-to-human transmission (Guangdong, China).

Transmission of SARS-CoV is primarily from person to person. It appears to have occurred mainly during the second week of illness, which corresponds to the peak of virus excretion in respiratory secretions and stool, and when cases with severe disease start to deteriorate clinically. Most cases of human-to-human transmission occurred in the health care setting, in the absence of adequate infection control precautions. Implementation of appropriate infection control practices brought the global outbreak to an end.

Nature of the disease

Symptoms are influenza-like and include fever, malaise, myalgia, headache, diarrhoea, and shivering (rigors). No individual symptom or cluster of symptoms has proved to be specific for a diagnosis of SARS. Although fever is the most frequently reported symptom, it is sometimes absent on initial measurement, especially in elderly and immunosuppressed patients.

Cough (initially dry), shortness of breath, and diarrhoea are present in the first and/or second week of illness. Severe cases often evolve rapidly, progressing to respiratory distress and requiring intensive care.

Geographical distribution

The distribution is based on the 2002–2003 epidemic. The disease appeared in November 2002 in the Guangdong province of southern China. This area is considered as a potential zone of re-emergence of SARS-CoV.

Other countries/areas in which chains of human-to-human transmission occurred after early importation of cases were Toronto in Canada, Hong Kong Special Administrative Region of China, Chinese Taipei, Singapore, and Hanoi in Viet Nam.

Risk for travellers

Currently, no areas of the world are reporting transmission of SARS. Since the end of the global epidemic in July 2003, SARS has reappeared four times – three times from laboratory accidents (Singapore and Chinese Taipei), and once in southern China where the source of infection remains undetermined although there is circumstantial evidence of animal-to-human transmission.

Should SARS re-emerge in epidemic form, WHO will provide guidance on the risk of travel to affected areas. Travellers should stay informed about current travel recommendations. However, even during the height of the 2003 epidemic, the overall risk of SARS-CoV transmission to travellers was low.

Prophylaxis

None. Experimental vaccines are under development.

The National Institute of Health (NIH) states:

The virus that causes coronavirus disease 2019 (COVID-19) is stable for several hours to days in aerosols and on surfaces, according to a new study from National Institutes of Health, CDC, UCLA and Princeton University scientists in The New England Journal of Medicine. The scientists found that severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) was detectable in aerosols for up to three hours, up to four hours on copper, up to 24 hours on cardboard and up to two to three days on plastic and stainless steel. The results provide key information about the stability of SARS-CoV-2, which causes COVID-19 disease, and suggests that people may acquire the virus through the air and after touching contaminated objects. The study information was widely shared during the past two weeks after the researchers placed the contents on a preprint server to quickly share their data with colleagues.

The NIH scientists, from the National Institute of Allergy and Infectious Diseases’ Montana facility at Rocky Mountain Laboratories, compared how the environment affects SARS-CoV-2 and SARS-CoV-1, which causes SARS. SARS-CoV-1, like its successor now circulating across the globe, emerged from China and infected more than 8,000 people in 2002 and 2003. SARS-CoV-1 was eradicated by intensive contact tracing and case isolation measures and no cases have been detected since 2004. SARS-CoV-1 is the human coronavirus most closely related to SARS-CoV-2. In the stability study the two viruses behaved similarly, which unfortunately fails to explain why COVID-19 has become a much larger outbreak.

The NIH study attempted to mimic virus being deposited from an infected person onto everyday surfaces in a household or hospital setting, such as through coughing or touching objects. The scientists then investigated how long the virus remained infectious on these surfaces.

The scientists highlighted additional observations from their study:

  • If the viability of the two coronaviruses is similar, why is SARS-CoV-2 resulting in more cases? Emerging evidence suggests that people infected with SARS-CoV-2 might be spreading virus without recognizing, or prior to recognizing, symptoms. This would make disease control measures that were effective against SARS-CoV-1 less effective against its successor.
  • In contrast to SARS-CoV-1, most secondary cases of virus transmission of SARS-CoV-2 appear to be occurring in community settings rather than healthcare settings.  However, healthcare settings are also vulnerable to the introduction and spread of SARS-CoV-2, and the stability of SARS-CoV-2 in aerosols and on surfaces likely contributes to transmission of the virus in healthcare settings.

The findings affirm the guidance from public health professionals to use precautions similar to those for influenza and other respiratory viruses to prevent the spread of SARS-CoV-2:

  • Avoid close contact with people who are sick.
  • Avoid touching your eyes, nose, and mouth.
  • Stay home when you are sick.
  • Cover your cough or sneeze with a tissue, then throw the tissue in the trash.
  • Clean and disinfect frequently touched objects and surfaces using a regular household cleaning spray or wipe.

QUOTE FOR TUESDAY:

The CDC states:

“-Seasonal influenza (flu) vaccines are designed to protect against the three influenza viruses that are expected to circulate most widely during the upcoming season.

-CDC is working with other federal agencies and the private sector, to improve flu vaccine technologies.

-Three different flu vaccine production technologies are FDA approved for use in the United States: egg-based flu vaccine, cell-culture based flu vaccine, and recombinant flu vaccine.

Influenza (flu) vaccines cause antibodies to develop in the body about two weeks after vaccination. These antibodies provide protection against infection with the influenza viruses that are used to make vaccine. The seasonal flu vaccine protects against the influenza viruses that research suggests will be most common during the upcoming season. These include three different main groups of influenza Type A and B viruses.”

Center for Disease Control and Prevention – CDC (How Influenza (Flu) Vaccines Are Made | Influenza (Flu) | CDC&Different Types of Flu Vaccines | Influenza (Flu) | CDC)

QUOTE FOR MONDAY:

THE CDC STATES:

  • “The week ending January 25, 2024, was the first time that the percent of deaths for influenza (1.7%) was higher than the percent of deaths for COVID-19. The percent of deaths for influenza has continued to increase and is 2.6% for the week ending February 8, 2025.
  • Eleven pediatric deaths associated with seasonal influenza virus infection were reported this week, bringing the 2024-2025 season total to 68 pediatric deaths.
  • CDC estimates that there have been at least 29 million illnesses, 370,000 hospitalizations, and 16,000 deaths from flu so far this season.
  • CDC recommends that everyone ages 6 months and older get an annual influenza (flu) vaccine.1
  • There are prescription flu antiviral drugs that can treat flu illness; those should be started as early as possible and are especially important for patients at higher risk for severe illness.2
  • Influenza viruses are among several viruses contributing to respiratory disease activity. CDC is providing updated, integrated information about COVID-19, flu.”

Center for Disease Control and Prevention – CDC (Weekly US Influenza Surveillance Report: Key Updates for Week 6, ending February 8, 2025 | FluView | CDC)

QUOTE FOR THE WEEKEND:

“A significant challenge for diagnosing women with heart disease is the lack of recognition of symptoms that might be related to heart disease, or that don’t fit into classic definitions. Women can develop symptoms that are subtler and harder to detect as a heart attack, especially if the physician is only looking for the “usual” heart attack symptoms.

“Women are much more likely to have atypical heart attack symptoms,” says Dr. Lili Barouch, director of the Johns Hopkins Columbia Heart Failure Clinic. “So while the classical symptoms, such as chest pains, apply to both men and women, women are much more likely to get less common symptoms such as indigestion, shortness of breath, and back pain, sometimes even in the absence of obvious chest discomfort.

The first step to lowering cardiovascular risk is to raise your awareness of the risk factors and symptoms that are particular to women. The next step is to take actions and practice daily behaviors that lower the risk factors you can control.”

John Hopkins Medicine (Heart Disease: Differences in Men and Women | Johns Hopkins Medicine)


QUOTE FOR FRIDAY:

It shouldn’t come as a surprise that there are several deadly diseases that strike Blacks harder and more often than they do other groups, particularly whites.  There are reasons like genetic, lifestyle, diet with activities of daily living.

“Here are some of the diseases affecting African Americans the most:

1-60% more common in Blacks than in whites. Blacks are up to 2.5 times more likely to suffer a limb amputation and up to 5.6 times more likely to suffer kidney disease than other people with diabetes.

2-The death reflected a harsh reality in the United States: Asthma hits African-Americans particularly hard, and the health care system often fails them. An estimated 15.3 percent of black children have the disease compared with 7.1 percent of white children, according to the Centers for Disease Control and Prevention. Overall, African-Americans are nearly three times as likely to die from asthma as white people.

3-You may not hear it much, but deaths from lung scarring — sarcoidosis — are 16 times more common among Blacks than among whites.

4-Strokes kill 4 times more 35- to 54-year-old Black Americans than white Americans. Blacks have nearly twice the first-time stroke risk of whites.

Black Americans have a higher prevalence of stroke and higher death rate from stroke than any other racial group. Stroke is a “brain attack” that most often occurs when blood that brings oxygen to your brain stops flowing and brain cells die.

5-One of the significant risk factors for heart disease is high blood pressure. Blacks develop high blood pressure earlier in life — and with much higher blood pressure levels — than whites. According to The American Heart Association, the prevalence of high blood pressure in African Americans is the highest in the world. African American adults are 40% more likely to have high blood pressure than non-Hispanic whites.

The National Institutes of Health is changing this situation. One reason for this change — as research into lung disease, heart disease, and diabetes shows — is the growing realization that the health of Black Americans isn’t a racial issue, but a human issue.”

BlackDoctor.org

(The 7 Deadliest Diseases in the Black Community – BlackDoctor.org – Where Wellness & Culture Connect)

Part I Black History Month — Read about common diseases in this ethnic group.

Figure 2: Black Population, by State, 2010-2011

The majority of Americans black or white under 67.5 have to work to have medical coverage (unless under disability), if not the majority of Americans would be rich.

Health care disparities heighten disease differences between African-Americans and white Americans.

  • African-Americans are three times more likely to die of asthma than white Americans.
  • Diabetes is 60% more common in black Americans than in white Americans. Blacks are up to 2.5 times more likely to suffer a limb amputation and up to 5.6 times more likely to suffer kidney disease than other people with diabetes.
  • Deaths from lung scarring — sarcoidosis — are 16 times more common among blacks than among whites. The disease recently killed former NFL star Reggie White at age 43.
  • Despite lower tobacco exposure, black men are 50% more likely than white men to get lung cancer.
  • Strokes kill 4 times more 35- to 54-year-old black Americans than white Americans. Blacks have nearly twice the first-time stroke risk of whites.
  • Blacks develop high blood pressure earlier in life — and with much higher blood pressure levels — than whites. Nearly 42% of black men and more than 45% of black women aged 20 and older have high blood pressure.
  • Cancer treatment is equally successful for all races. Yet black men have a 40% higher cancer death rate than white men. African-American women have a 20% higher cancer death rate than white women.

Why?

Factor 1 – Genes definitely play a role. So does the environment in which people live, socioeconomic status,  says Clyde W. Yancy, MD, associate dean of clinical affairs and medical director for heart failure/transplantation at the University of Texas Southwestern Medical Center.

Living in a low socioeconomic environment puts you at risk to eating fast foods or deli food (especially in the cities) and increasing, over long term eating fast foods, causing disease (DM, Obesity, Heart Disease and could go on).

Factor 2 – Another reason is that a higher percentage of black Americans than white Americans live close to toxic waste dumps — and to the factories that produce this waste.

Addressing socioeconomic groups first, Dr. Yancy says that all humans have the same physiology, are vulnerable to the same illnesses, and respond to the same medicines. Naturally, diseases and responses to treatment do vary from person to person. But, he says, there are unique issues that affect black Americans.

Like Yancy, LeRoy M. Graham Jr., MD, says the time is ripe for Americans to come to grips with these issues. Graham, a pediatric lung expert, serves on the American Lung Association’s board of directors, is associate clinical professor of pediatrics at Morehouse School of Medicine in Atlanta, and serves as staff physician for Children’s Healthcare of Atlanta.

“I just think we as physicians need to get more impassioned,” Graham tells WebMD. “There are health disparities. There are things that may have more sinister origins in institutionalized racism. But we as doctors need to spend more time recognizing these disparities and addressing them — together with our patients — on a very individual level.”

A 2005 report from the American Lung Association shows that black Americans suffer far more lung disease than white Americans do.

Some of the findings:

  • Black Americans have more asthma than any racial or ethnic group in America. And blacks are 3 times more likely to die of asthma than whites.
  • Black Americans are 3 times more likely to suffer sarcoidosis than white Americans. The lung-scarring disease is 16 times more deadly for blacks than for whites.
  • Black American children are 3 times as likely as white American children to have sleep apnea.
  • Black American babies die of sudden infant death syndrome (SIDS) 2.5 times as often as white American babies.
  • Black American men are 50% more likely to get lung cancer than white American men.  For starters this race is highier overall than caucasians in smoking in the U.S.A.
  • Black Americans are half as likely to get flu and pneumonia vaccinations as white Americans.

“The environment is involved, and there is potential genetic susceptibility — but we also have to talk about the fact that African-Americans’ social and economic status lags behind that of Caucasians,” Graham says. “And low socioeconomic status is linked to more disease.”

Of course these 2 factors put you at risk for disease, but you want to live in a better environment do your research.   Some may say it due to blacks being treated poorly or the word “racism”.  Is this the case, No not at all.  You need the facts why you blacks are highier in living in a toxic or low socioeconomic group.  One, that is where they can afford and decide to live their. Two is because they feel they can not or they decide not to move due to personal reasons like lack to apply self to get in a better environment (whether it be due to fear, lack of knowing their success in the move/challenge so they don’t want to take the chance or not wanting change and decide to stay in that toxic or low socio-economic area.  No one puts a magnum 45 to anyone’s head telling them they have to stay in these areas.  In America you can live where you want.  So its up to the individual with the family having the will to make the move in their life to be less exposed to areas poor for you health.  Its up to them to research areas less expensive or better enviroment exposure areas in America; no one else is going to do that for them or any one else.  Than there are those that simply don’t mind living in areas like toxic or low socioeconomic exposed but many don’t understand that thinking.  The risk is that individual and their family put themselves at risk for a higher chance of getting these diseases like lung cancer, heart disease, etc…   Make the move and get out of those places and live a better quality of life for you and all in your family.  Its all up to you to make the move.  Keep in mind disease is not just environmental related.  You need to look at all factors like genetic, the diet you are on, how active you are; its not just one factor in most cases.  You have to take a holistic approach on seeing what diseases you could be exposed to and why.  Don’t wait till symptoms start finding out its possibly too late.  Think PREVENTION over treatment.  Its your life and up to you!

Part II tomorrow