
Archive | November 2023
QUOTE FOR WEDNESDAY:
“Based on fair evidence, excessive salt intake and deficient dietary consumption of fresh fruits and vegetables are associated with an increased risk of gastric cancer. Dietary intake of vitamin C contained in vegetables, fruits, and other foods of plant origin is associated with a reduced risk of gastric cancer. Diets high in whole-grain cereals, carotenoids, allium compounds, and green tea are also associated with a reduced risk of this cancer. However, it is uncertain if changing one’s diet to include more vegetables, fruits, and whole grains would reduce the risk of gastric cancer.”
National Cancer Society (https://www.cancer.gov/types/stomach/hp/stomach-prevention-pdq)
Part III National Stomach Cancer Awareness Month – How to prevent it and treatments!

Measures for Prevention of Stomach (Gastric) Cancer Risk:
Smoking cessation
Based on solid evidence, smoking is associated with an increased risk of stomach cancer. The 2004 Surgeon General’s report identifies cigarette smoking as a cause of stomach cancer, with an average relative risk (RR) in former smokers of 1.2 and in current smokers of 1.6. Compared with persistent smokers, the risk of stomach cancer decreases among former smokers with time since cessation. This pattern of observations makes it reasonable to infer that cigarette smoking prevention or cessation would result in a decreased risk of gastric cancer.
H. pylori infection eradication
Based on solid evidence, H. pylori infection is associated with an increased risk of gastric cancer.
Treat stomach infections. If you have ulcers from an H. pylori infection, get treatment. Antibiotics can kill the bacteria, and other drugs will heal the sores in the lining of your stomach to cut your risk of cancer.
Diet
Eat healthy. Get more fresh fruits and vegetables on your plate every day. They’re high in fiber and in some vitamins that can lower your cancer risk. Avoid very salty, pickled, cured, or smoked foods like hot dogs, processed lunch meats, or smoked cheeses. Keep your weight at a healthy level, too. Being overweight or obese can also raise your risk of the disease.
Based on fair evidence, excessive salt intake and deficient dietary consumption of fresh fruits and vegetables are associated with an increased risk of gastric cancer. Dietary intake of vitamin C contained in vegetables, fruits, and other foods of plant origin is associated with a reduced risk of gastric cancer. Diets high in whole-grain cereals, carotenoids, allium compounds, and green tea are also associated with a reduced risk of this cancer. However, it is uncertain if changing one’s diet to include more vegetables, fruits, and whole grains would reduce the risk of gastric cancer.
TREATMENTS FOR STOMACH CANCER:
Many treatments can fight stomach cancer. The one you and your doctor choose will depend on how long you’ve had the disease or how much it has spread in your body, called the stage of your cancer.
Surgery. Your doctor might remove part of your stomach or other tissues nearby that have cancer cells. Surgery gets rid of the tumor and stops cancer from spreading to other parts of your body. If your disease is in a more advanced stage, your doctor might need to remove all of your stomach=Gastrectomy or in some other cases the Surgeon may only have to remove part of the stomach=Partial Gastrectomy.
Some tumors can keep food from moving in and out of your stomach. In that case, you might have surgery to put in a stent, a device that keeps the pathways open.
Chemotherapy. Drugs kill your cancer cells or keep them from growing. You can take them as pills or through an IV at a clinic. Chemo usually takes several weeks. The drugs can cause side effects, but your doctor can help you find ways to feel better during treatment.
Radiation. High-energy waves or particles can kill cancer cells and shrink tumors. Your doctor may use an X-ray or other machine to beam radiation at the spot where your tumor is.
Chemoradiation. Your doctor might use this mix of chemotherapy and radiation to shrink your tumor before surgery.
Targeted drugs. These newer drugs are different because they fight only cancer cells. Other treatments, like chemo and radiation, can kill healthy cells along with diseased ones. As a result, targeted therapies have fewer side effects than these other treatments.
QUOTE FOR TUESDAY:
“Stomach cancer is the fifth most common cancer worldwide. It is more common in countries in East Asia, Eastern Europe, and South and Central America than in the United States and other Western countries. There are many known risk factors for stomach cancer (also called gastric cancer), but often it’s not clear exactly how these factors might affect how cells in the stomach become cancer cells. This is the subject of ongoing research.”
American Cancer Society (https://www.cancer.org/cancer/types/stomach-cancer/causes-risks-prevention/what-causes.html)
Part II National Stomach Cancer Awareness Month – Risk Factors!

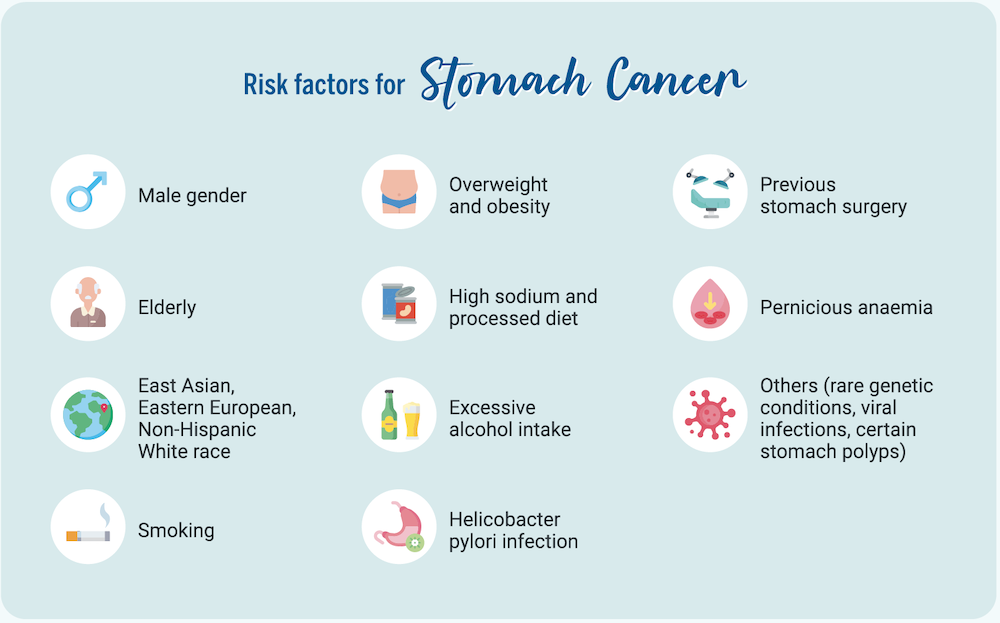
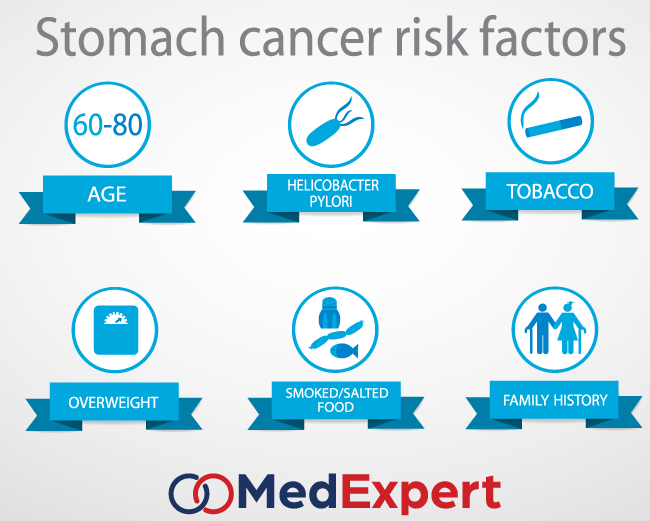
RISK FACTORS FOR STOMACH CANCER:
GENERAL
- Age: Stomach cancer is found most often in people over age 55.
- Gender: The disease affects men twice as often as women.
- Race: Stomach cancer is more common in African Americans than in Caucasians.
- Region: This type of cancer is more common in some parts of the world, such as Japan, Korea, parts of Eastern Europe and Latin America. People in these areas eat many foods that are preserved by drying, smoking, salting or pickling.
BODY
- Obesity: Obesity has been linked to an increased risk of stomach cancer
GENETICS
Certain gene mutations and some inherited conditions are considered stomach cancer risk factors. They include:
- BRCA1 & BRCA2: Inherited mutations on the BRCA1 and BRCA2 genes are often associated with higher risks for breast cancer. Individuals who have inherited these genetic mutations are also at an increased risk for stomach cancer
- E-cadherin/CDH1: Though rare, people who inherit this genetic mutation have a 70 to 80 percent chance of developing stomach cancer in their lifetime. Also, women with this genetic defect have an increased risk of breast cancer.
- Lynch syndrome: This condition may also be referred to as hereditary non-polyposis colorectal cancer (HNPCC), a genetic condition that runs in families. More commonly, this condition is associated with an increased risk for colon cancer. HNPCC also predisposes people to stomach cancers.
- Familial adenomatous polyposis (FAP): This syndrome causes polyps in the colon, stomach and intestines. Often caused by mutations of the gene APC, this syndrome greatly increases a person’s risk of colorectal cancer and may play a small role in increasing a person’s stomach cancer risk.
LIFESTYLE
- Smoking: There is evidence linking cigarette smoking to many types of cancer, including stomach cancer. Smokers have been found to be at greater risk of developing cancer than non-smokers.
- Diet: Scientists believe that eating foods preserved in these ways may play a role in the development of stomach cancer. On the other hand, fresh foods (especially fresh fruits and vegetables and properly frozen or refrigerated fresh foods) may protect against this disease.
- Working in the coal, metal or rubber industries: Chemicals that are released in these environments have been linked to the development of stomach cancer.
OTHER CONDITIONS
- H. pylori infection: Doctors have found that a long-term H. pylori infection may lead to inflammation and pre-cancerous changes to the stomach lining. In fact, stomach cancer patients typically have a higher incidence of H. pylori infections than people who do not have stomach cancer.
- Pernicious anemia: Some people with pernicious anemia may have gastric polyps, which can increase the risk of stomach cancer.
- Epstein-Barr virus infection: According to the American Cancer Society, Epstein-Barr virus is found in the cancer cells of about 5% to 10% of people with stomach cancer.
ENVIRONMENTAL AND OCCUPATIONAL EXPOSURES
The risk of stomach cancer is increased in people who
-
work in the rubber or coal industry
-
have been exposed to very high levels of radiation
Those at risk for Stomach Cancer:
People at elevated risk for gastric cancer include older adults with atrophic gastritis or pernicious anemia; patients with sporadic gastric adenomas, familial adenomatous polyposis, or hereditary nonpolyposis colon cancer; and immigrant ethnic populations from countries with high rates of gastric carcinoma. Workers in the rubber and coal industries are also at increased risk.
There is consistent evidence that Helicobacter pylori infection, also known as H. pylori infection, of the stomach is strongly associated with both the initiation and promotion of carcinoma of the gastric body and antrum and of gastric lymphoma.
There is consistent and solid evidence that Epstein-Barr virus (EBV) infection is strongly associated with gastric cancer.
Compared with the general population, people with duodenal ulcer disease may have a lower risk of gastric cancer.
Risk factors for gastric cancer include the presence of precursor conditions such as chronic atrophic gastritis and intestinal metaplasia, pernicious anemia, and gastric adenomatous polyps. Risk factors could include type A blood type. Environmental factors include low consumption of fruits and vegetables; consumption of salted, smoked, or poorly preserved foods; cigarette smoking; and radiation exposure.
Those at great increased risk for stomach cancer:
Hereditary diffuse gastric cancer (HDGC) is a rare inherited condition in which people have a greatly increased risk of stomach cancer, which often develops at a fairly early age. This rare syndrome is most often caused by an inherited mutation in the CDH1 gene.
It’s very important to recognize people and families with this inherited syndrome, because most people who have it will develop stomach cancer. Families with HDGC typically have two or more close relatives who develop stomach cancer (usually the diffuse type), and/or at least one person who is diagnosed before age 50. Some family members might also develop invasive lobular breast cancer.
Doctors often refer people who might have HDGC to a genetics professional, so they can discuss possibly getting genetic testing. If testing is done and shows a person has a mutation (abnormal change) in the CDH1 gene, doctors often recommend they consider having their stomach removed (typically between the ages of 20 and 30) before cancer develops. However, this operation (called a total gastrectomy) can lead to long-term changes in the way a person eats.
Some other hereditary cancer syndromes are also linked with an increased risk for stomach cancer, including Lynch syndrome, familial adenomatous polyposis (FAP), Li-Fraumeni syndrome, and Peutz-Jeghers syndrome. The risk of stomach cancer with these syndromes is not nearly as high as it is with HDGC, so removal of the stomach is not typically recommended for people who have these syndromes.
QUOTE FOR MONDAY:
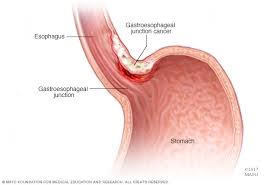
“Stomach cancer can happen in any part of the stomach. In most of the world, stomach cancers happen in the main part of the stomach. This part is called the stomach body.
In the United States, stomach cancer is more likely to start by the gastroesophageal junction. This is the part where the long tube that carries food you swallow meets the stomach. The tube that carries food to the stomach is called the esophagus.
There is adenocarcinoma stomach cancer, gastrointestinal stromal tumors (GIST), carcinoid tumors – that are found in many area of the body that start in your neuroendocrine cells, and lymphoma is a cancer that starts in immune system cells. Most lymphomas that start in the stomach are a type of non-Hodgkin’s lymphoma.”
MAYO CLINIC (https://www.mayoclinic.org/diseases-conditions/stomach-cancer/symptoms-causes/syc-20352438)
Part I National Stomach Cancer Awareness Month – types and symptoms!

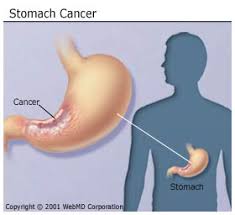
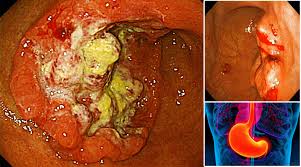
Stomach cancer (also called gastric cancer) can develop in any part of the stomach, and may spread throughout the stomach and to other organs. It may grow along the stomach wall into the esophagus or small intestine.
The cancer may also extend through the stomach wall and spread to nearby lymph nodes and organs, such as the liver, pancreas and colon. It may spread to distant organs, such as the lungs, the lymph nodes above the collarbone and to a woman’s ovaries.
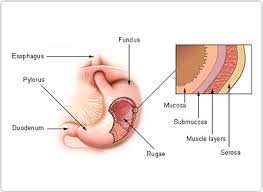
Stomach cancer happens when cells start behaving abnormally, growing and proliferating uncontrollably. The stomach, a hollow organ that collects food and breaks it down, has five different parts—from the top of the stomach, which connects to the esophagus, to the bottom of the stomach, which connects to the small intestine:
- Cardia, the area nearest to the esophagus
- Fundus, the upper stomach
- Corpus, the main body of the stomach
- Antrum, where food gets broken down by stomach acid
- Pylorus, which connects to the small intestine
There are also five layers of tissue and muscle that surround the stomach and make up the stomach wall. Going from inner to outer, the layers are:
- Mucosa
- Submucosa
- Muscularis propria
- Subserosa
- Serosa
Stomach cancer progressively spreads through these different layers. Establishing how far within the stomach wall the cancer has spread is a part of the staging process (LIKE all cancers), which determines how serious the cancer is and how best to treat it.
The mucosa layer, which produces stomach acid, is where most stomach cancers begin.
A less common type of stomach cancer is caused by gastrointestinal stromal tumors (GISTs), which start in immature cells called interstitial cells of Cajal.
Other rare stomach cancer types, such as lymphoma and neuroendocrine tumors, start in different cell types in the stomach.
Different types of stomach cancer include:
- Adenocarcinomas develop within the cells of the innermost lining of the stomach. The majority of stomach cancers are classified as adenocarcinomas.Most stomach cancer cases, about 90 percent to 95 percent, are adenocarcinomas, according to the American Cancer Society (ACS).Adenocarcinomas are broken down into two categories:
- Intestinal adenocarcinomas are usually slow-growing and more treatable. Oftentimes, these cancers may be treated with therapy drugs that are designed to target specific mutations in cancer cells. This type most often occurs in men and older adults.
- Diffuse adenocarcinomas are less common than intestinal adenocarcinomas and usually more aggressive. They tend to be faster growing, often spreading (metastasizing) to other parts of the body quickly. This type is more common at a younger age than intestinal adenocarcinomas.
- Lymphoma is a cancer of the immune system tissue that may start anywhere there are lymph tissues, including the stomach. However, lymphomas in the stomach are rare, accounting for about 4 percent of all stomach cancers. MALT (mucosa-associated lymphoid tissue) lymphoma is a type of non-Hodgkin lymphoma that typically occurs in the stomach. The cancer starts in lymph tissue that lines the stomach.
- Gastrointestinal stromal tumors, or GISTs, are a rare type of stomach cancer that starts in a special cell found in the lining of the stomach called interstitial cells of Cajal (ICCs). Under a microscope, GIST cells look similar to muscle or nerve cells. These tumors may develop throughout the digestive tract, but about 60 to 70 percent occur in the stomach. In the United States, 4,000 to 6,000 new GIST cases throughout the GI tract are diagnosed per year, according to the ACS.
- Carcinoid tumors typically start in the hormone producing cells of the stomach. These tumors usually do not spread to different organs and account for only about 3 percent of stomach cancer incidence. About 8,000 gastrointestinal carcinoid tumors are diagnosed in the United States each year, according to the ACS. Not all of these cancers start in the stomach—they may also occur in the intestines, appendix, colon and rectum.
Early stage cancers especially adenocarcinoma(s) may cause:
- Indigestion
- Bloating
- Nausea
- Poor appetite
- Heartburn
As these cancers advanced, they may cause:
- Bloody stool
- Vomiting
- Unexplained weight loss
- Belly pain
- Jaundice (yellowing of the skin and eyes)
- Difficulty swallowing
QUOTE FOR THE WEEKEND:
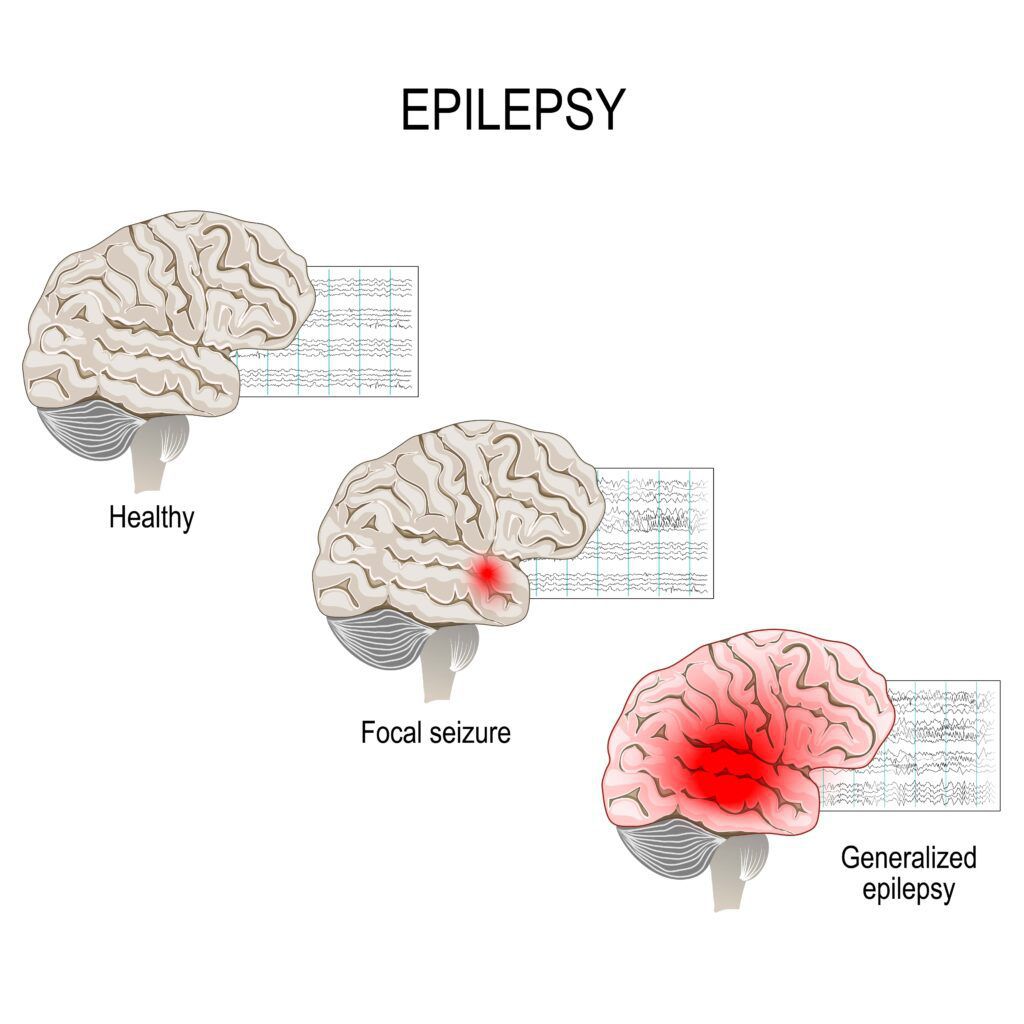
“An estimated 65 million people worldwide have epilepsy, and one in 26 Americans will develop epilepsy in their lifetime. Most of these people are able to control their seizures with medications, but approximately 30% to 40% have what’s called drug-resistant or medically refractory epilepsy, in which they don’t respond to standard anti-seizure medications. There are a few options available for people with drug-resistant epilepsy who need alternative RXs. The most common alternative one is epilepsy surgery, which has been performed since the 1940s. For a patient with focal epilepsy, where the seizures are being caused by one part of the brain, you try to remove the seizure focus. Somewhere between 60% and 70% of patients with drug-resistant epilepsy who have this surgery become seizure-free, which is the standard of care if the medications were not to work. Open brain surgery is effective but also carries higher risk for complications, pain and psychological impacts. Recently, minimally invasive epilepsy brain surgery has advanced quite significantly, particularly a procedure called laser ablation for patients with epilepsy. In that surgery, inserted is a small laser fiber and burn away the seizure focus in the brain but an opening up of the skull is not needed.”
UChicago Medicine (https://www.uchicagomedicine.org/forefront/neurosciences-articles/new-treatment-options-for-people-with-drug-resistant-epilepsy)
QUOTE FOR FRIDAY:
“Epilepsy is sometimes referred to as a long-term condition, as people often live with it for many years, or for life. Although generally epilepsy cannot be ‘cured’, for most people, seizures can be ‘controlled’ (stopped) so that epilepsy has little or no impact on their lives. So treatment is often about managing seizures in the long-term.
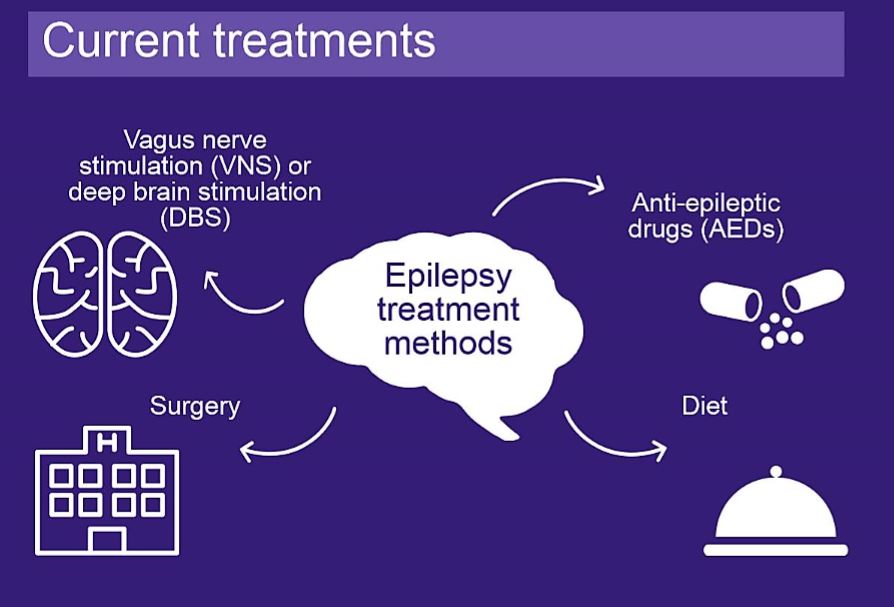
Most people with epilepsy take anti-seizure medication (ASM), previously known as anti-epileptic drugs or AEDs, to stop their seizures from happening. However, there are other treatment options for people whose seizures are not controlled by ASM.”
Epilepsy Society (https://epilepsysociety.org.uk/about-epilepsy/treatment)
PART IV Epilepsy – Treatments for Epilepsy Disorders – Medications 1st!
Treatments for Epilepsy:
1.) Medications:
Anti-seizure medication works best if taken regularly, around the same time each day. The aim of treatment is to stop all of your seizures with the lowest dose of the fewest number of ASMs and with the least side effects. Usually treatment starts using a single ASM at a low dose, which is increased slowly (called titration), until your seizures are controlled. Titration meaning the MD first starts you on a therapeutic dose for you age and body weight. If the dosage is not working he or she will increase till control of the seizure is accomplished. If your seizures are not controlled with this drug, a different ASM is usually tried (by adding in the new drug and then slowly withdrawing the first one, again doing titration-you can never stop ASMs abruptly since you would be at a high risk of a seizure). If your seizures are not controlled with a single drug, another drug might be added, so that you take two different ASMs each daye, which is not uncommon.
Most people’s seizures last the same length of time each time they happen and usually stop by themselves. However, sometimes seizures do not stop or one seizure follows another without the person recovering in between. When a seizure goes on for 5 minutes or more it is called status epilepticus (or ‘status’ for short).
Status during a tonic clonic (convulsive) seizure is a medical emergency and needs urgent treatment. Emergency medication is usually prescribed(like Valium through a IV site to do a intravenous push) to stop seizures once they have started and if they are going on longer than usual, or if someone has one seizure after another without recovering in between they maybe on a IV drip with IVPs till controlled. Specialist training is needed to give emergency medication.
Than there are also Medication trials:
At any time, a patient may be invited to participate in a trial of an experimental medication. Since about 1993, this is how all medications have received FDA approval. Often, patients are invited to join a trial after they have failed a number of other FDA-approved medications.
The advantages of participating in a clinical trial include:
● Access to new medication
● Close support and follow-up with the epilepsy team
● The opportunity to help medical researchers develop new treatments
The goal of medication clinical trials is to make sure the drugs are safe and effective. Clinical trials are experimental studies, so there is some risk involved with participating. However, clinical research teams follow extremely strict federal, state, and hospital guidelines to ensure that the risks are minimized.
Since there are so many anti-epilepsy drugs (AEDs) out there, it can get confusing talking to your doctor and pharmacist about them. Here is a list of seizure medications listed to help you understand the seven most widely used Anti-epileptic Drugs-AEDs in the US that are FDA approved.
7 most common seizure medications used for epilepsy:
When you are first diagnosed with epilepsy, your doctor will usually try to treat the condition with medication. The seven AEDs in this list are the most common ‘first line’ medications used for different kinds of epilepsy.
For some people, these ‘first line’ drugs work right away. But for others, the AED either doesn’t work, or the seizure medication side effects are very unpleasant. If so, their doctor will normally try an alternative medicine. For about one-third of people with epilepsy, medication doesn’t work. Fortunately, there are other treatment options available.
1. Valproic Acid
Brand names: Depakote, Depakene
Form: Can be taken as tablets, liquids, or granules (sprinkled on food)
Treats: Generalized, focal, absence – effective with most kinds of epilepsy
Since being introduced in 1978, Valproic Acid has become the most widely prescribed AED in the world. You will usually take it once or twice per day, in varying doses, depending on your age and weight.
Valproic Acid works by making it hard for your brain cells to work as fast, which means they can’t ‘fire’ off as much during a seizure.
2. Lamotrigine
Brand names: Lamictal
Form: Comes as tablets you can swallow or chew
Treats: Generalized (tonic clonic) seizures; atonic seizures
Lamotrigine is a widely used seizure medication among people with generalized epilepsy. You’ll take the tablets once or twice per day. It works by slowing down the bursts of electrical signals in the brain that happen during a seizure. Lamotrigine appears to be one of the safer AEDs to take during pregnancy – unlike many other AED medications.
3. Topiramate
Brand names: Topamax
Form: Comes as tablets to swallow
Treats: Generalized (tonic clonic) seizures; atonic seizures; Lennox-Gastaut syndrome
Topiramate is mainly used to treat generalized epilepsy. You’ll usually take the tablets twice per day. Like with other AEDs, it works by slowing down how fast your brain cells work, which helps stop seizures from developing. It should not be used if you are pregnant.
4. Carbamazepine
Brand names: Tegretol, Curatil
Form: Comes as tablets, liquids and suppositories
Treats: Focal seizures
Carbamazepine is a sodium channel blocker which was first approved to treat epilepsy in 1968. Sodium ion channels work a bit like gates in the brain, so by blocking them carbamazepine slows down how quickly signals get sent. It should not be used if you are pregnant.
5. Phenytoin
Brand names: Dilantin
Form: Comes as tablets for swallowing or chewing tablet and as a liquid
Treats: Focal seizures
Phenytoin was first approved by the FDA in 1939. It is believed to work by blocking sodium ion channels in the brain, and therefore stops high frequency firing of electric signals in the brain.
6. Oxcarbazepine
Brand names: Trileptal, Oxtellar XR
Form: Comes as tablets form, or as a liquid
Treats: Focal seizures
Oxcarbazepine is used to treat focal seizures and comes in quick and slow release forms. It’s not fully known how this AED works, but it’s believed that it blocks sodium channels in the brain.
7. Ethosuximide
Brand names: Zarontin
Form: Comes as tablets for or as a liquid
Treats: Absence seizures
Ethosuximide is a seizure medicine which is mainly used for the treatment of absence seizures, especially for children. We still don’t know quite how it works, but it seems to stop brain cells from firing so fast.
Over the past hundred years, scientists have discovered many powerful and effective AEDs which help many people lead seizure-free lives. These advances are great news for the epilepsy community as a whole. But many people who take AEDs find that they just don’t work for them – about one third of people have “refractory epilepsy”, which means they’ve tried two or more AEDs without being able to control their seizures. So about 30 percent or slight more of epilepsy patients unfortunately do not respond to their AED meds.
The good news is that there are several alternative ways of treating epilepsy if AEDs don’t seem to work. These include special diets and medical devices. Ending line alternate treatment levels of controlling Epilepsy! That is this weekend’s topic, Hurray!