Archive | October 2023

QUOTE FOR WEEKEND:

“Exposure to acetaminophen in the womb may increase a child’s risk for attention deficit/hyperactivity disorder and autism spectrum disorder, suggests a study funded by the National Institutes of Health and the Agency for Health Care Research and Quality.”

NIH National Institute of Health (https://www.nih.gov/news-events/news-releases/nih-funded-study-suggests-acetaminophen-exposure-pregnancy-linked-higher-risk-adhd-autism)


QUOTE FOR FRIDAY:

“People were followed for periods ranging from three to 11 years, depending on the study, using questionnaires, interviews, and self-reports on medication use.The analysis revealed a 20% higher risk of autism and a 30% higher risk of ADHD for children who had prolonged exposure to acetaminophen during fetal development.

However, it noted that taking small amounts of acetaminophen during pregnancy — in one study, for fewer than eight days — didn’t increase risks.

Other studies since then have supported earlier findings that too much acetaminophen may increase one’s risk for autism and ADHD.”

Cleveland Clinic (https://health.clevelandclinic.org/pregnancy-does-acetaminophen-heighten-risks-for-autism-adhd/)


QUOTE FOR THURSDAY:

“Acetaminophen is one of the most commonly used drugs during pregnancy globally. Recent studies have reported associations between prenatal exposure to acetaminophen and neurobehavioral problems in children, including attention-deficit hyperactivity disorders. Little research has investigated these associations in preschool-age children or the potential confounding effects of prenatal stress.  Acetaminophen use during pregnant may also disrupt the maternal and fetal gut microbiota leading to neurodevelopmental problems [18, 19]. Another possible mechanism of the association between prenatal acetaminophen use and neurobehavioral problems in childhood is prenatal stress.”

National Library of Medicine (https://www.ncbi.nlm.nih.gov/pmc/articles/PMC9518858/)


Tylenol and fetal effects when taken during pregnancy!

Harvard Health Publishing states the following

“For years, products containing acetaminophen, such as the pain reliever Tylenol, were largely viewed as safe to take during pregnancy. Hundreds of widely available over-the-counter remedies, including popular cold, cough, and flu products, contain acetaminophen. Not surprisingly, some 65% of women in the US report taking it during pregnancy to relieve a headache or to ease an aching back.

But recently, a group of doctors and scientists issued a consensus statement in Nature Reviews Endocrinology urging increased caution around acetaminophen use in pregnancy. They noted growing evidence of its potential to interfere with fetal development, possibly leaving lingering effects on the brain, reproductive and urinary systems, and genital development. And while the issue they raise is important, it’s worth noting that the concerns come from studies done in animals and human observational studies. These types of studies cannot prove that acetaminophen is the actual cause of any of these problems.

Acetaminophen is known to be an endocrine disruptor. That means it can interfere with chemicals and hormones involved in healthy growth, possibly throwing it off track.

According to the consensus statement, some research suggests that exposure to acetaminophen during pregnancy — particularly high doses or frequent use — potentially increases risk for early puberty in girls, or male fertility problems such as low sperm count. It is also associated with other issues such as undescended testicles, or a birth defect called hypospadias where the opening in the tip of the penis is not in the right place. It might play a role in attention deficit disorder and negatively affect IQ.

Risks for ill effects are low

If you took acetaminophen during a current or past pregnancy, this might sound pretty scary — especially since you’ve probably always considered this medicine harmless. But while experts agree it’s important to consider potential risks when taking any over-the-counter or prescription medicines during pregnancy, you shouldn’t panic.

“The risk for an individual is low,” says Dr. Kathryn M. Rexrode, chief of the Division of Women’s Health, Department of Medicine at Harvard-affiliated Brigham and Women’s Hospital.

Chances are pretty good that if you took acetaminophen during a pregnancy, your baby likely did not, or will not, suffer any ill effects.

The research on this topic is not conclusive. Some information used to inform the consensus statement was gathered from studies on animals, or human studies with significant limitations. More research is needed to confirm that this medicine is truly causing health problems, and to determine at what doses, and at what points during a pregnancy, exposure to acetaminophen might be most harmful.

Sensible steps if you’re pregnant

Three common-sense steps can help protect you and your baby until more is known on this topic:

  • Avoid acetaminophen during pregnancy when possible. Previously during preconception and pregnancy counseling, Dr. Rexrode had warned patients against using NSAID drugs, such as Advil and Aleve, and suggested taking acetaminophen instead. “Now I also tell people that some concerns have been raised about acetaminophen use during pregnancy, and explain that its use should be limited to situations where it is really needed,” says Dr. Rexrode. In short, always consider whether you really need it before you swallow a pill.
  • Consult with your doctor. Always clear acetaminophen use with your doctor, particularly if you are going to be using the medicine for a long period of time. They might agree that taking it is the best option — or suggest a safer alternative.
  • Minimize use. If you do need to take acetaminophen during pregnancy, take it for the shortest amount of time possible and at the lowest effective dose to reduce fetal exposure. “This advice about the lowest necessary dose for the shortest period of time is generally good counseling for all over-the-counter medication use, especially during pregnancy,” says Dr. Rexrode.

While all of this is good advice for using acetaminophen, there are times when it’s riskier not to take it. For example, if you have a high fever during pregnancy — which can harm your baby — acetaminophen may be needed to bring your fever down. Provided it’s advised by your doctor, the benefits of acetaminophen use in this case outweigh the potential risks.”

Harvard Health Publishing is the media and publishing division of the Harvard Medical School of Harvard University, under the direction of Dr. David H. Roberts, Dean for External Education.


QUOTE FOR WEDNESDAY:

“Stroke is the third most common overall cause of death and the leading cause of adult disability in the United States. New therapeutic interventions instituted in the period immediately after a stroke have revolutionized the approach to ischemic cerebrovascular disease. Recognition of a transient ischemic attack provides an opportunity to prevent a subsequent stroke. Specific stroke prevention treatment depends on the cause of the transient ischemic attack, its cerebrovascular localization and the presence of associated coexisting medical problems. Modification of stroke risk factors is the principal therapeutic approach. Antiplatelet agents and anticoagulants have been shown to be effective in reducing the occurrence of stroke in certain populations.”

American Family Physician (https://www.aafp.org/pubs/afp/issues/1999/1115/p2329.html)

QUOTE FOR TUESDAY:

“Choose face paint and makeup whenever possible instead of masks, which can obstruct a child’s vision.  Popular trick-or-treating hours are 5:30 p.m. to 9:30 p.m. Be especially alert for kids during those hours.  Join kids under age 12 for trick-or-treating. If kids are mature enough to be out without supervision, tell them to stick to familiar areas that are well lit and trick-or-treat in groups.”

SAFE KIDS Worldwide (https://www.safekids.org/tip/halloween-safety-tips)

QUOTE FOR MONDAY:

“Here’s a scary statistic: Children are more than twice as likely to be hit by a car and killed on Halloween than on any other day of the year. Lack of visibility because of low lighting at night also plays a factor in these incidents.  A responsible adult should accompany young children on the neighborhood round.  If your older children are going alone, plan and review a route acceptable to you. Agree on a specific time children should return home.  Watch for children walking on roadways, medians and curbs.  Enter and exit driveways and alleys carefully.  All costumes, wigs and accessories should be fire-resistant.  If children are allowed out after dark, fasten reflective tape to their costumes and bags, or give them glow sticks.”

National Safety Council NSC (https://www.nsc.org/community-safety/safety-topics/seasonal-safety/autumn-safety/halloween)


QUOTE FOR THE WEEKEND:

“The two mRNA vaccines produced by Moderna and Pfizer-BioNTech using the original SARS-CoV-2 virus have proved to be effective at reducing severe disease, even against omicron. “The existing vaccines are doing an absolutely terrific job of keeping people out of hospital, out of ICU, and alive,” says Sten Vermund, MD, PhD, an infectious disease epidemiologist, and professor at the Yale School of Public Health and a pediatrician at Yale School of Medicine in New Haven, Connecticut.

Under the direction of the Food and Drug Administration (FDA), Pfizer-BioNTech and Moderna have started clinical trials of bivalent vaccines targeting BA.4 and BA.5, which have nearly identical spike proteins. This means that the vaccine will be a mixture of the original vaccine and one that has been reformulated to target the mutated spike proteins of the now-dominant subvariants.

All vaccines approved by stringent regulatory agencies (SRAs) or with WHO Emergency Use Listing (EUL) are safe and effective at reducing the risk of severe disease and death due to COVID-19 infection.

Please remember that the benefits of COVID-19 vaccinations outweigh the risks of getting severely ill with COVID-19. If you are able to get vaccinated, do not delay it. Getting vaccinated could save your life.

Read more on different types of COVID-19 vaccines here.

For the latest information on vaccines, please visit the ‘What you need to know’ pages for AstraZeneca, Covaxin, Johnson and Johnson (J&J),  Moderna, Novavax, Pfizer, Sinopharm and Sinovac.”

WHO World Health Organization (https://www.who.int/news-room/questions-and-answers/item/coronavirus-disease-(covid-19)-vaccines)

So why get COVID vaccinated after reading Friday’s topic; THERE IS A REASON TO GET IT!

The WHO-World Health Org. states the following

( News 12/09/2022):

“Getting vaccinated could save your life. COVID-19 vaccines have saved millions of lives since their introduction and provide strong protection against serious illness, hospitalization and death.

It is still possible to get COVID-19 and spread it to others after being vaccinated. Therefore, consider continuing to practice protective and preventive behaviours such as keeping a distance, wearing a mask in crowded and poorly ventilated spaces, practicing hand hygiene, respiratory etiquette (covering your mouth and nose with a bent elbow or a tissue when you cough or sneeze), getting vaccinated and staying up to date with booster doses. However, if you do get COVID-19 after vaccination, you are more likely to have mild or no symptoms than if you hadn’t been vaccinated.

Even if you have had COVID-19, WHO still recommends that you get vaccinated after infection because vaccination enhances your protection against severe outcomes of future COVID-19 infection, and you may be protected for longer. Furthermore, hybrid immunity resulting from vaccine and infection may provide superior protection against existing variants of concern.

To ensure optimal protection, is important to receive COVID-19 vaccine doses and boosters recommended to you by your health authority.

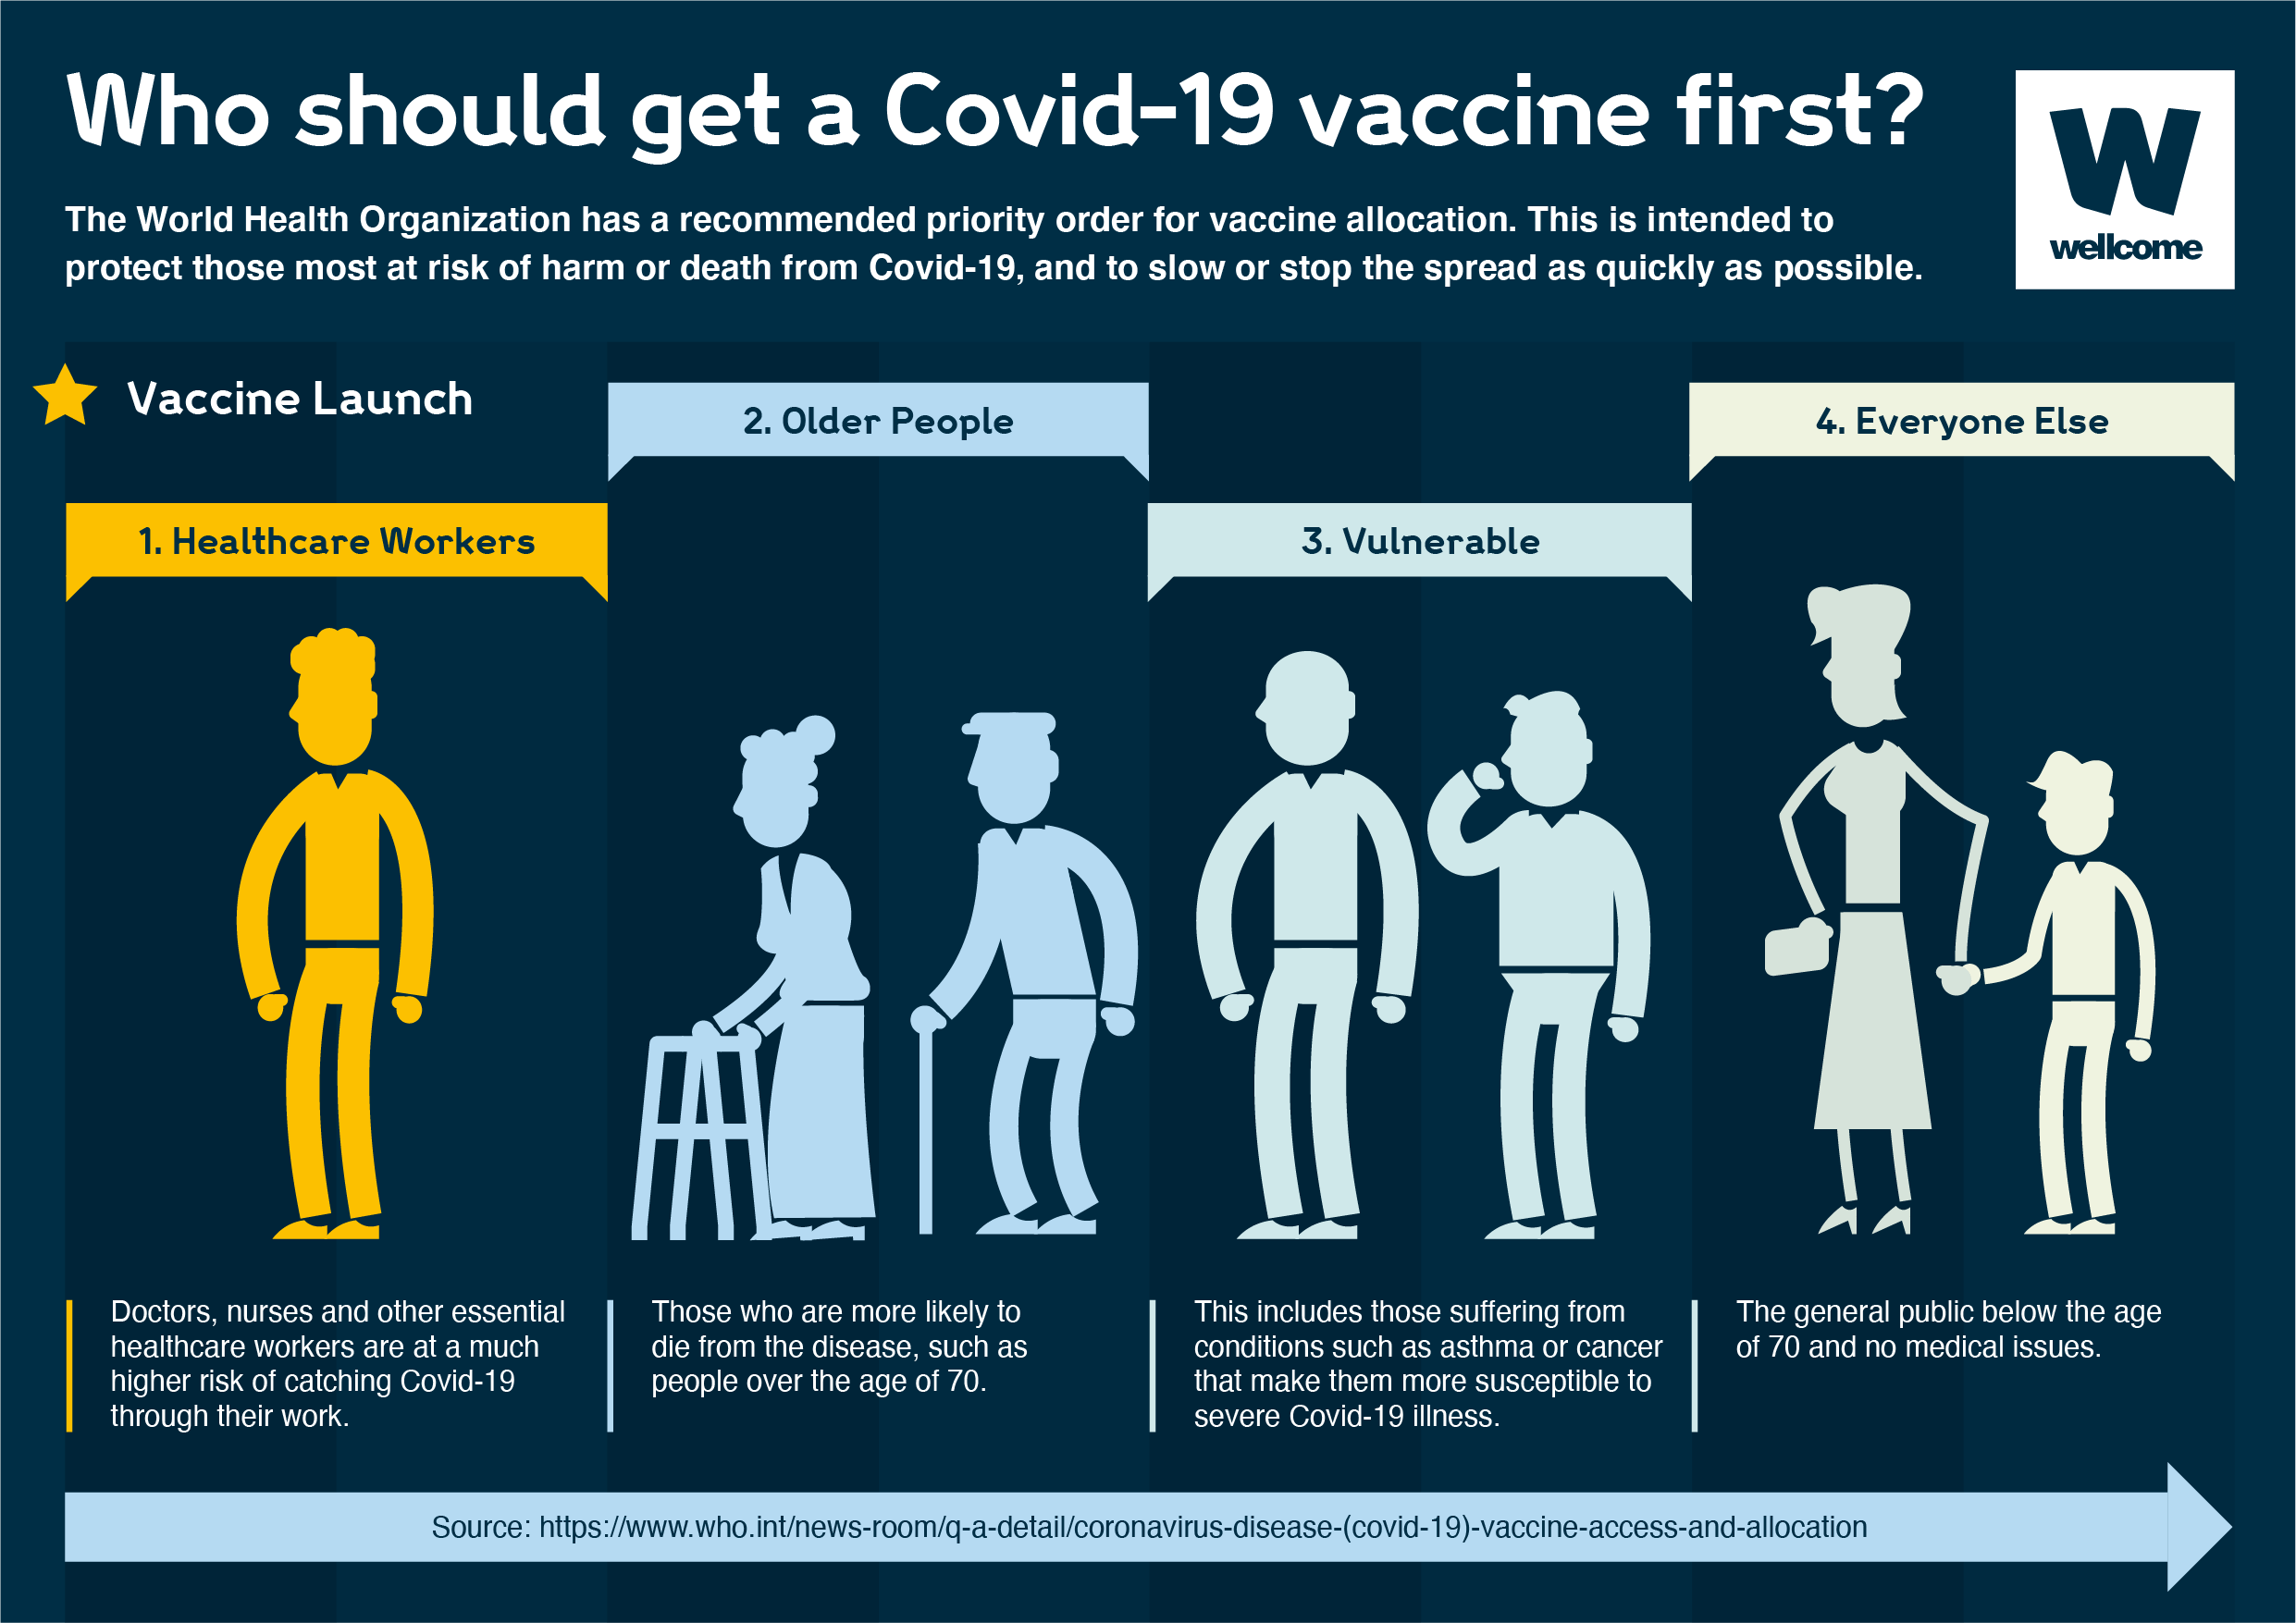
The high-priority group should be prioritized for the primary series vaccines as well as first and additional booster doses. The additional boosters should be administered either 6 or 12 months (depending on your risk category) after the last dose, with the timeframe depending on factors such as age and immunocompromising conditions.

The medium-priority group includes healthy adults – usually under the age of 50–60 without comorbidities, and children and adolescents with comorbidities. SAGE recommends primary series and first booster doses for the medium-priority group. Although additional boosters are safe for this group, SAGE does not routinely recommend them, given the comparatively low public health returns.

The low-priority group includes healthy children and adolescents aged 6 months to 17 years. Primary and booster doses are safe and effective in children and adolescents. However, considering the low burden of disease, SAGE urges countries considering vaccination of this age group to base their decisions on contextual factors, such as the disease burden, cost-effectiveness, and other health or programmatic priorities and opportunity costs.”

So after all this information with all these Vaccines this gives 2 questions?

1-With the new ones now available, WHICH ONE IS BETTER? 

2-Which immunity is better: Disease-induced immunity (you had covid and were induced with immunity) or vaccination-induced (immunity by the vaccine itself)?

It turns out it’s not in either  situation. Limitations exist with gaining immunity either way – BUT  in by getting infected by the virus (disease induced) and by getting vaccinated.

Previous research indicated that disease-induced immunity wasn’t necessarily better and that vaccines created more effective and longer-lasting immunity than natural immunity. Disease-induced immunity, specifically, can be spotty and appears to be somewhat related to how severe the illness was (more severely ill persons appear to have a greater immune response than those with very mild illness or asymptomatic infection). Some people may have a good antibody response, while others don’t get much of any response.

The additional benefit of vaccine-induced immunity? Fewer downsides. 

  • Both immunity types start to wane within 60 to 90 days, depending on how your body reacts
  • Getting the virus comes with more risks, including the potential to develop severe illness, long-COVID or death

Vaccination helps protect against the most serious risks. “Yes, the vaccine has a few rare serious adverse events associated with it,” says infectious diseases expert Mark Rupp, MD. “However, the risk of adverse events is much lower than the substantial risks of serious infection and the risk of long-COVID that you get with the disease.”

Studies now show that both types of immunity are beneficial.

“Recent data analyses indicate that disease-induced immunity can be as long-lasting or even longer-lasting in some instances than vaccine-induced immunity,” adds Dr. Rupp. “Both appear to do a pretty good job protecting from severe illness and death.”

The best protection against severe outcomes: Hybrid immunity

Hybrid immunity = natural immunity + vaccination

According to an analysis published in The Lancet Infectious Diseases, a recent, robust study shows that hybrid immunity is longer lasting and more effective than disease-induced immunity or vaccination alone.

Which immunity is better: Disease-induced immunity or vaccination-induced immunity?

It turns out it’s not an either-or situation. Limitations exist with gaining immunity either way – by getting infected by the virus (disease induced) and by getting vaccinated.

Previous research indicated that disease-induced immunity wasn’t necessarily better and that vaccines created more effective and longer-lasting immunity than natural immunity. Disease-induced immunity, specifically, can be spotty and appears to be somewhat related to how severe the illness was (more severely ill persons appear to have a greater immune response than those with very mild illness or asymptomatic infection). Some people may have a good antibody response, while others don’t get much of any response.

The additional benefit of vaccine-induced immunity? Fewer downsides. 

  • Both immunity types start to wane within 60 to 90 days, depending on how your body reacts
  • Getting the virus comes with more risks, including the potential to develop severe illness, long-COVID or death

Vaccination helps protect against the most serious risks. “Yes, the vaccine has a few rare serious adverse events associated with it,” says infectious diseases expert Mark Rupp, MD. “However, the risk of adverse events is much lower than the substantial risks of serious infection and the risk of long-COVID that you get with the disease.”

Studies now show that both types of immunity are beneficial.

“Recent data analyses- indicate that disease-induced immunity can be as long-lasting or even longer-lasting in some instances than vaccine-induced immunity,” adds Dr. Rupp. “Both appear to do a pretty good job protecting from severe illness and death.”

The best protection against severe outcomes: Hybrid immunity

Hybrid immunity = natural immunity + vaccination

According to an analysis published in The Lancet Infectious Diseases, a recent, robust study shows that hybrid immunity is longer lasting and more effective than disease-induced immunity or vaccination alone.

THE WHO further states (News 12/09/2022):

“EMA’s human medicines committee (CHMP) has recommended authorising an adapted bivalent vaccine targeting the Omicron subvariants BA.4 and BA.5 in addition to the original strain of SARS-CoV-2. This recommendation will further extend the arsenal of available vaccines to protect people against COVID-19 as the pandemic continues and new waves of infections are anticipated in the cold season.”

First B-4 and B-5  or known also as 4-5 COVID-19 vaccines) for use as a booster dose in individuals aged 12 years and older. The new bivalent vaccine comprises 15 micrograms of famtozinameran based on the Omicron variants BA. 4 and BA. 5, and 15 micrograms of tozinameran based on the original strain of SARS CoV-2.

Through the European Medicines Agency (https://www.ema.europa.eu/en/news/adapted-vaccine-targeting-ba4-ba5-omicron-variants-original-sars-cov-2-recommended-approval) they state the following:

“EMA’s human medicines committee (CHMP) has recommended authorising an adapted bivalent vaccine targeting the Omicron subvariants BA.4 and BA.5 in addition to the original strain of SARS-CoV-2. This recommendation will further extend the arsenal of available vaccines to protect people against COVID-19 as the pandemic continues and new waves of infections are anticipated in the cold season.

Comirnaty Original/Omicron BA.4-5 is for use in people aged 12 years and above who have received at least a primary course of vaccination against COVID-19. This vaccine is an adapted version of the mRNA COVID-19 vaccine Comirnaty (Pfizer/BioNTech).

Vaccines are adapted to better match the circulating variants of SARS-CoV-2 and are expected to provide broader protection against different variants. Prompt assessment of the available data on these adapted vaccines will enable their timely deployment in the autumn vaccination campaigns.

In its decision to recommend the authorisation of Comirnaty Original/Omicron BA.4-5, the CHMP took into account all the available data on Comirnaty and its adapted vaccines, including the recently authorised adapted vaccine Comirnaty Original/Omicron BA.1 as well as investigational vaccines against other variants of concern.

The CHMP based its opinion in particular on the clinical data available with Comirnaty Original/Omicron BA.1. Apart from containing mRNA matching different, but closely related, Omicron subvariants, Comirnaty Original/Omicron BA.4-5 and Comirnaty Original/Omicron BA.1 have the same composition. Clinical studies with Comirnaty Original/Omicron BA.1 showed that the vaccine was more effective at triggering an immune response against the BA.1 subvariant than Comirnaty, and was as effective as Comirnaty against the original strain. Side effects were comparable to those seen with Comirnaty. This was further supported by data from investigational vaccines targeting other variants which have also shown similar safety profiles and predictable immune responses against the strains they target.

The CHMP’s opinion for Comirnaty Original/Omicron BA.4-5 is also based on data on its quality and manufacturing process, which confirmed that it meets the EU standards for quality. In addition, immunogenicity data (the ability of the vaccine to trigger an immune response) from laboratory (non-clinical) studies provided supportive evidence that Comirnaty Original/Omicron BA.4-5 triggers adequate immunity against the strains it targets.

Based on all these data, the CHMP concluded that Comirnaty Original/Omicron BA.4-5 is expected to be more effective than Comirnaty at triggering an immune response against the BA.4 and BA.5 subvariants. The vaccine’s safety profile is expected to be comparable to that of Comirnaty Original/Omicron BA.1, and of Comirnaty itself for which a large amount of data is available.”




QUOTE FOR FRIDAY:

“Within two decades, there have emerged three highly pathogenic and deadly human coronaviruses, namely SARS-CoV, MERS-CoV and SARS-CoV-2. The economic burden and health threats caused by these coronaviruses are extremely dreadful and getting more serious as the increasing number of global infections and attributed deaths of SARS-CoV-2 and MERS-CoV. Unfortunately, specific medical countermeasures for these hCoVs remain absent. Moreover, the fast spread of misinformation about the ongoing SARS-CoV-2 pandemic uniquely places the virus alongside an annoying infodemic and causes unnecessary worldwide panic. SARS-CoV-2 shares many similarities with SARS-CoV and MERS-CoV, certainly, obvious differences exist as well. Lessons learnt from SARS-CoV and MERS-CoV, timely updated information of SARS-CoV-2 and MERS-CoV, and summarized specific knowledge of these hCoVs are extremely invaluable for effectively and efficiently contain the outbreak of SARS-CoV-2 and MERS-CoV. By gaining a deeper understanding of hCoVs and the illnesses caused by them, we can bridge knowledge gaps, provide cultural weapons for fighting and controling the spread of MERS-CoV and SARS-CoV-2, and prepare effective and robust defense lines against hCoVs that may emerge or reemerge in the future”

Respiratory Research (https://respiratory-research.biomedcentral.com/articles/10.1186/s12931-020-01479-w)